<?xml version="1.0" encoding="utf-8"?><feed xmlns="http://www.w3.org/2005/Atom" ><generator uri="https://jekyllrb.com/" version="3.10.0">Jekyll</generator><link href="https://www.julianklug.com/feed.xml" rel="self" type="application/atom+xml" /><link href="https://www.julianklug.com/" rel="alternate" type="text/html" /><updated>2026-01-02T20:33:58+00:00</updated><id>https://www.julianklug.com/feed.xml</id><title type="html">JK</title><subtitle>MD</subtitle><author><name>Julian Klug</name></author><entry><title type="html">Research in Context: Machine learning for early dynamic prediction of functional outcome after stroke</title><link href="https://www.julianklug.com/posts/research/Reseach-in-context-OPSUM/" rel="alternate" type="text/html" title="Research in Context: Machine learning for early dynamic prediction of functional outcome after stroke" /><published>2024-11-18T00:00:00+00:00</published><updated>2024-11-18T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/research/Research-in-context-OPSUM</id><content type="html" xml:base="https://www.julianklug.com/posts/research/Reseach-in-context-OPSUM/"><![CDATA[<blockquote>
  <p><strong>Key Question</strong>: Can AI algorithms be used to monitor patients after acute ischemic stroke?</p>
</blockquote>

<p><strong>Evidence before this study</strong></p>

<p>Stroke is the most frequent cause of long-term disability in industrialized countries. To determine the best treatment and allocate the necessary resources, an early and accurate prediction is essential. Scores derived from logistic regression analysis and more recently from machine learning have been developed but are rarely used in clinical practice. We expand the review by Akay et al. from 20231, and searched MEDLINE for studies published in any language up to September 19th 2023, using the terms (“stroke” OR “cerebrovascular accident”) AND (“machine learning” OR “artificial intelligence” OR “neural network”) AND (“mortality” OR “survival” OR “rankin” OR “mRS”). We screened 557 articles, of which 71 were relevant for our study. We identified two main reasons that limit the clinical relevance of the current models. First, the large majority existing model were static using data collected only at admission. Only one single study by Hu et al from 2022 used four timepoints to construct time-specific models. However, no existing study used the most recent development in machine learning to develop dynamic prediction models, integrating continuous data that are recorded during the first days after stroke admission. The second reason that limits the use of existing machine learning model after stroke relate to their lack of transparency. In the management of patients, predictions that are not associated with mechanistic explanations show limited acceptance and come with legal and ethical challenges.</p>

<p><strong>Added value of this study</strong></p>

<p>We developed a novel machine learning approach to provide real-time predictions of mortality and good functional outcome in 2942 admissions for acute ischemic stroke. More specifically, we used a transformer model that was designed to integrate continuously recorded sequential data. During the first 72 hours after admission, our model was able to provide accurate hourly prediction of mortality at three months based on updated clinical, physiological, and biological data. This approach allows the model to make use not only of static values available at a given time, but also of temporal trends of all priorly obtained data. The model provided updated, real-time explanations of the variables driving the predictions. We were able to determine which features impact the prediction of mortality in an individual patient, at any given timepoint. To our knowledge, this is the first model providing dynamic hourly prediction of mortality after stroke.</p>

<p><strong>Implications of all the available evidence</strong></p>

<p>This study demonstrates the potential of machine learning models integrating multiple types of clinical, physiological, and biological variables over time after stroke. The good performance of our transformer model will certainly support the use of predictive models by clinicians who are traditionally reluctant to do so, current standard clinical care relying mostly on clinical knowledge and experience. The clinical applicability of our model will further be strengthened by access to hourly updated predictions along with accompanying explanations.</p>

<p><strong>References</strong></p>
<ol>
  <li>Akay, E. M. Z. et al. Artificial Intelligence for Clinical Decision Support in Acute Ischemic Stroke: A Systematic Review. Stroke 54, 1505–1516 (2023).</li>
</ol>

<p><em>Full paper</em>: Klug, J., Leclerc, G., Dirren, E. et al. Machine learning for early dynamic prediction of functional outcome after stroke. Commun Med 4, 232 (2024). 
https://www.nature.com/articles/s43856-024-00666-w</p>

<p><img src="/images/opsum/concept.webp" alt="Concept" title="Concept" /></p>]]></content><author><name>Julian Klug</name></author><category term="research" /><summary type="html"><![CDATA[Key Question: Can AI algorithms be used to monitor patients after acute ischemic stroke?]]></summary></entry><entry><title type="html">Can Pupillometry help to detect Delayed Cerebral Ischemia in SAH?</title><link href="https://www.julianklug.com/posts/research/Pupillometry-DCI/" rel="alternate" type="text/html" title="Can Pupillometry help to detect Delayed Cerebral Ischemia in SAH?" /><published>2024-07-31T00:00:00+00:00</published><updated>2024-07-31T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/research/Pupillometry-DCI</id><content type="html" xml:base="https://www.julianklug.com/posts/research/Pupillometry-DCI/"><![CDATA[<blockquote>
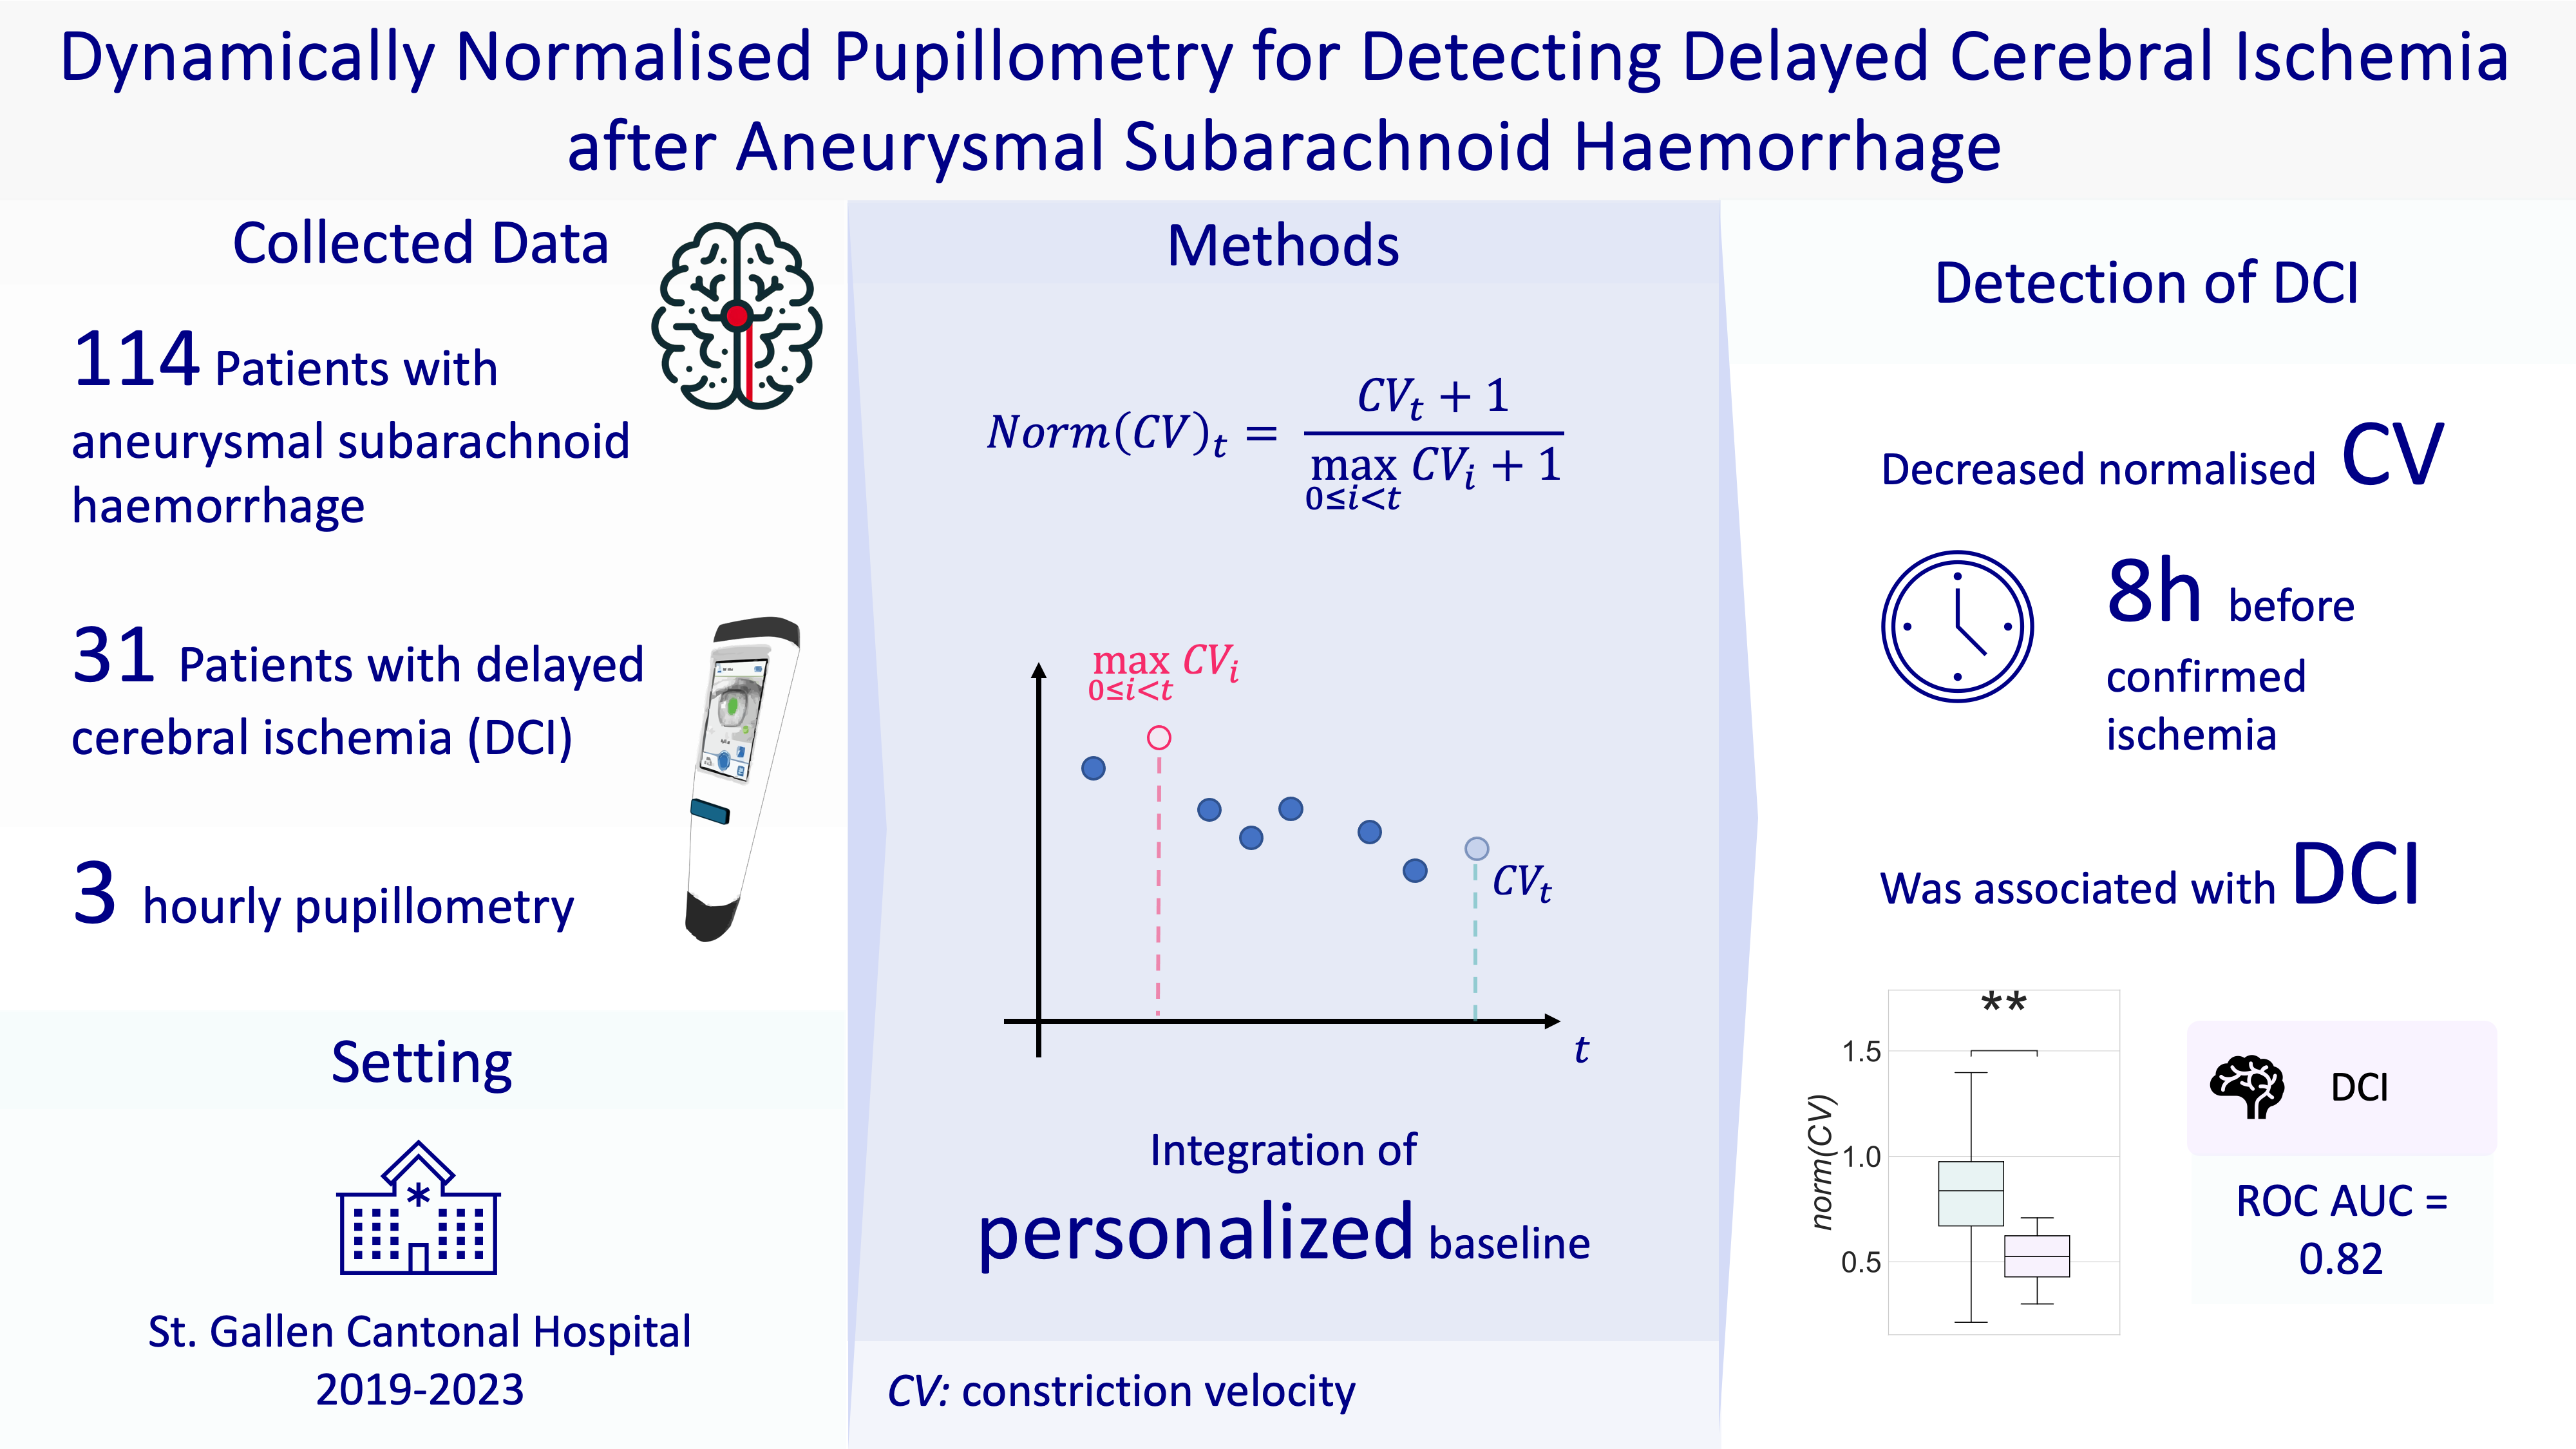
  <p><strong>Key Question</strong>: Can pupillometry be used to monitor and detect delayed cerebral ischemia (DCI) in patients with aneurysmal subarachnoid hemorrhage (aSAH)?</p>
</blockquote>

<p><img src="/images/pupillometry_dci/thumbnail.png" alt="Concept" title="Concept" /></p>

<p><strong>Context</strong> 
In patients with reduced state of consciousness or non-motor manifestations of ischemia such as confusion, the diagnosis of DCI is often complicated and the currently available tools are limited.</p>

<p><strong>Study Findings</strong> 
In this retrospective cohort study involving 114 patients with aSAH, we found that pupil constriction velocity (CV) normalized to each patient’s maximum recorded value since admission (referred to as normalized CV) was predictive of DCI within 8 hours. The predictive power was strong, with an area under the receiver operating characteristic curve (AUC) of 0.82. Other metrics, such as the Neurological Pupil Index (NPi) and non-normalized measures, were not significantly associated with DCI.
Study Details The study was conducted at the ICU of Cantonal Hospital St. Gallen in Switzerland, including all adult patients with aSAH admitted between March 2019 and December 2023. Pupillometry data was collected frequently (every 3 hours on average), allowing for continuous monitoring and normalization to each patient’s best recorded values. DCI was confirmed on perfusion CT.</p>

<p><strong>Features</strong></p>
<ul>
  <li>CV (constriction velocity): change in pupil size from baseline to minimum over time in response to a light-stimulus</li>
  <li>NPi (Neurological Pupil Index):  proprietary scalar index ranging from 0 to 5, with greater than or equal to 3 being a normal value</li>
  <li>Raw and normalized were evaluated</li>
</ul>

<p><strong>Why Normalize?</strong></p>
<ol>
  <li>Individual Baseline Differences: Normalization accounts for individual differences in baseline pupillary responses. Each patient has a unique baseline pupillary response, influenced by various factors such as the underlying neurological status, and side of initial injury. Normalizing allows comparisons to be made relative to each patient’s own optimal response rather than using a one-size-fits-all threshold.</li>
  <li>Dynamic Changes Over Time: Normalization helps in capturing the dynamic changes in pupillary function over time. In aSAH patients, the neurological state can fluctuate, and a normalized metric can sensitively reflect these changes. This is particularly important for conditions like DCI, which develop over time and may present subtly at first.</li>
</ol>

<p><strong>Results</strong></p>
<ul>
  <li>Predictive Value of Normalized CV: Normalized CV (inter-eye minimum, maximum in an 8-hour timebin) had an AUC of 0.82, indicating good discriminative ability. This metric was found to be the best predictor of DCI within an 8-hour window.</li>
  <li>Non-significance of NPi: The study confirmed that NPi and other non-normalized metrics were not significantly associated with DCI, supporting findings from previous research.</li>
  <li>Long-term Outcomes: Only CV, not NPi, was associated with long-term functional outcomes (measured by the modified Rankin Scale) at one year after adjusting for other factors.</li>
</ul>

<p><strong>Implications for Clinical Practice</strong> 
Normalized CV offers a new ancillary method for early detection of DCI in aSAH patients. This metric’s high sensitivity makes it a useful tool in the multimodal monitoring of patients, especially those who are sedated or cannot be clinically assessed.</p>

<p><strong>Conclusion</strong>
Frequent, longitudinal quantitative pupillometry, specifically normalized CV, can effectively predict DCI in aSAH patients. This method provides a personalized monitoring approach that could improve early detection and management of DCI, potentially enhancing patient outcomes.</p>

<p><em>Full paper</em>: Klug, Julian; Martins, Joana; De Trizio, Ignazio; Carrera, Emmanuel; Filipovic, Miodrag; Hostettler, Isabel Charlotte; Pietsch, Urs. Dynamically Normalized Pupillometry for Detecting Delayed Cerebral Ischemia After Aneurysmal Subarachnoid Hemorrhage. Critical Care Explorations 6(8):p e1135, August 2024. | DOI: 10.1097/CCE.0000000000001135 
https://journals.lww.com/ccejournal/fulltext/2024/08000/dynamically_normalized_pupillometry_for_detecting.2.aspx</p>

<p><img src="/images/pupillometry_dci/graphical_abstract.png" alt="Graphical abstract" title="Graphical abstract" /></p>]]></content><author><name>Julian Klug</name></author><category term="research" /><summary type="html"><![CDATA[Key Question: Can pupillometry be used to monitor and detect delayed cerebral ischemia (DCI) in patients with aneurysmal subarachnoid hemorrhage (aSAH)?]]></summary></entry><entry><title type="html">Generative AI for scientific illustration</title><link href="https://www.julianklug.com/posts/generative-ai-for-scientific-illustration" rel="alternate" type="text/html" title="Generative AI for scientific illustration" /><published>2024-06-11T00:00:00+00:00</published><updated>2024-06-11T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/generative-ai-for-scientific-illustration</id><content type="html" xml:base="https://www.julianklug.com/posts/generative-ai-for-scientific-illustration"><![CDATA[<p>Good illustrations are key for efficient scientific communication, education, and dissemination of knowledge. An image can easily convey complex concepts that are sometimes only cumbersomely captured in writing. In this light, more and more authors are making use of generative AI tools to create illustrations for their scientific publications.</p>

<p><img src="/images/generative_ai/prompt_input.png" alt="Prompt input" title="Waiting for your input" /></p>

<h3 id="on-the-importance-of-checking-model-output"><em>On the importance of checking model output</em></h3>

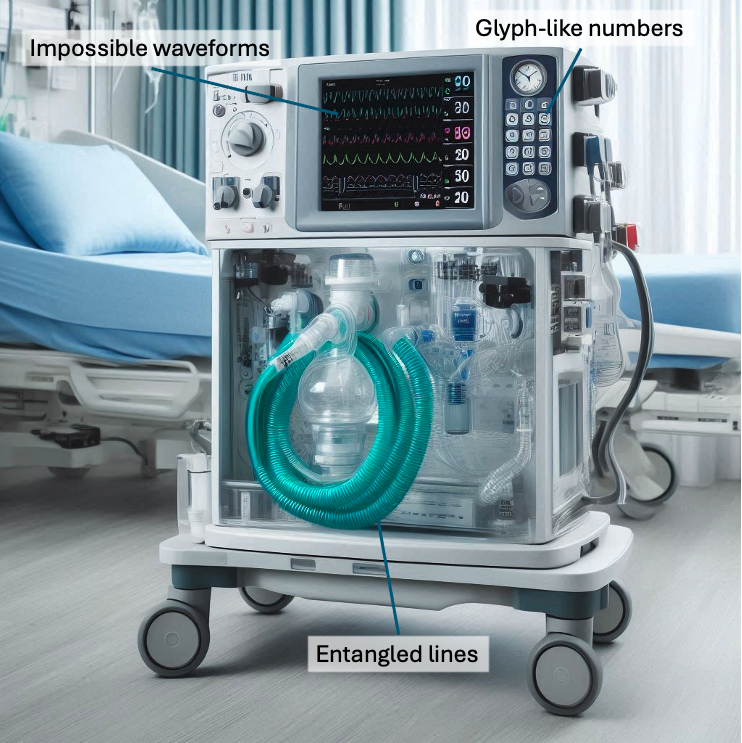
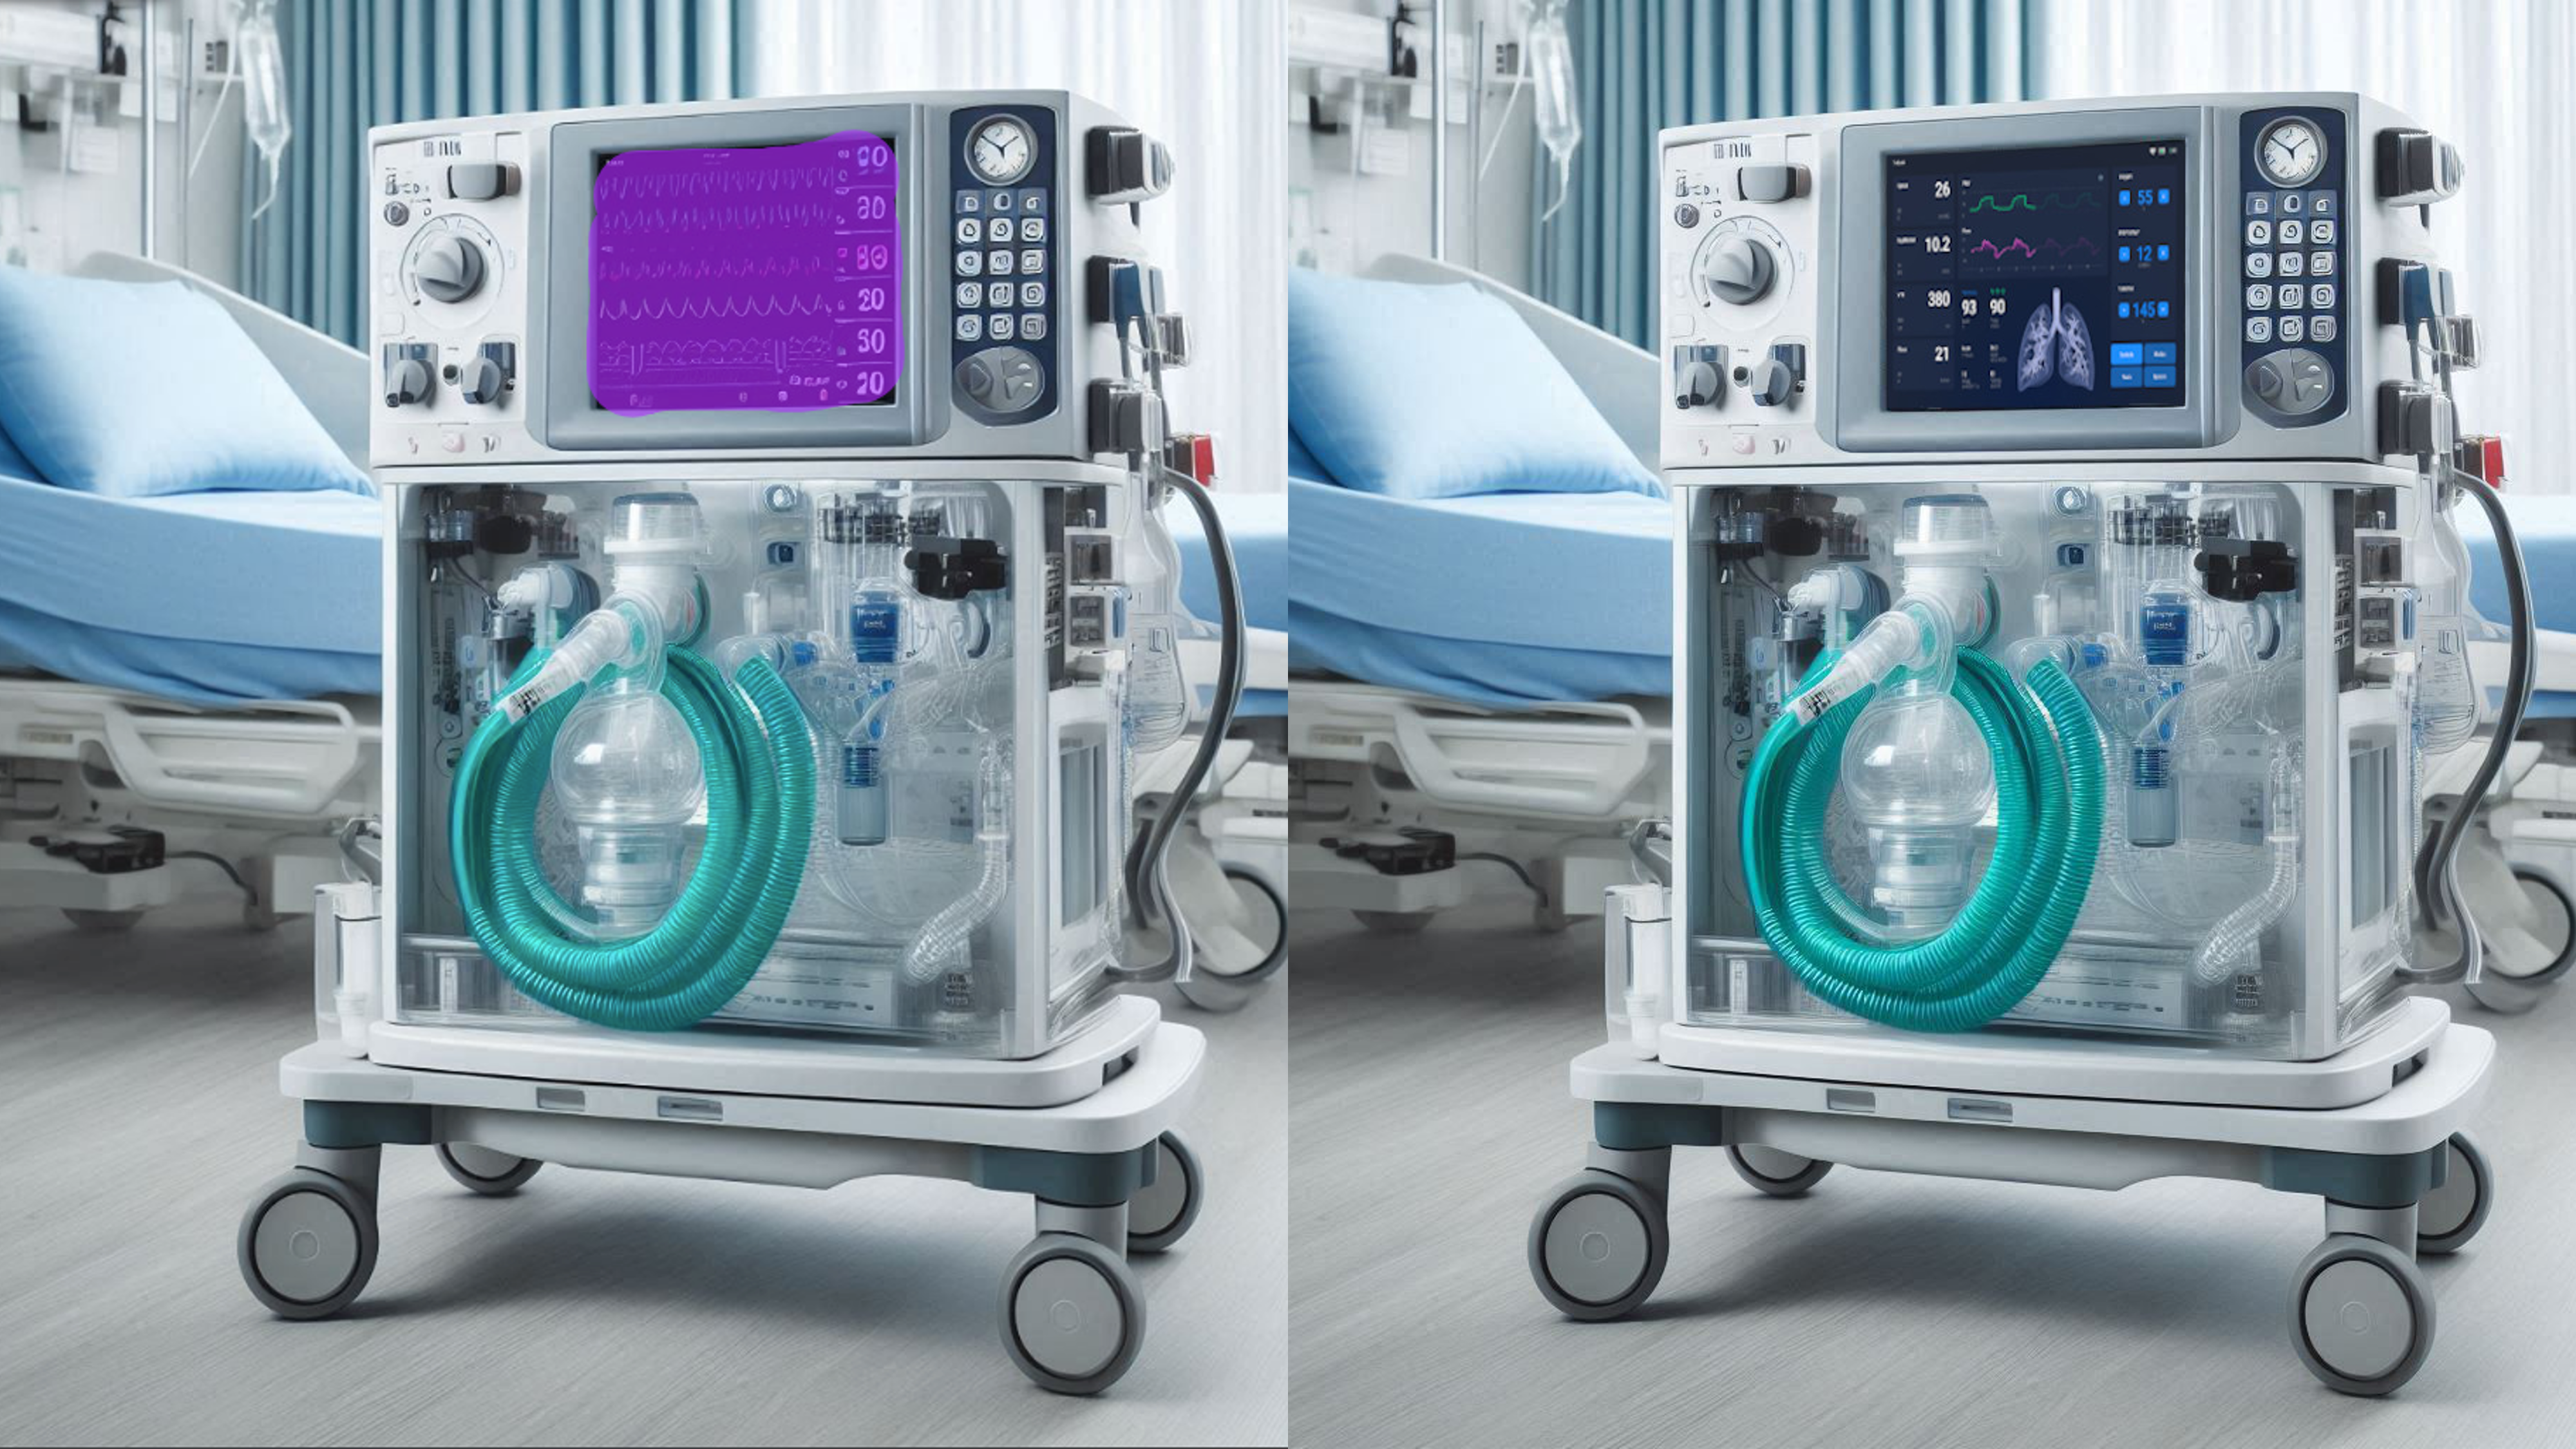
<p>With more and more illustrations created by AI, many inaccurate or misleading images are beeing published. Some with malicious intent <sup id="fnref:1" role="doc-noteref"><a href="#fn:1" class="footnote" rel="footnote">1</a></sup>, others due to lack of knowledge on how to use the tools. Do these small errors matter? I would argue, that they are the image equivalent of spelling errors. Although the overall message might still be conveyed, the reader might be distracted by the error, or even worse, misinterpret the image. As most scientist are not trained in image editing, they appear more difficult to correct than a spelling error. However, with the right chaining of tools, this can be done in a few minutes.</p>

<p><img src="/images/generative_ai/labeled_image.png" alt="Example of generated image" title="Labeled image" /></p>

<h3 id="the-iterative-process"><em>The iterative process</em></h3>

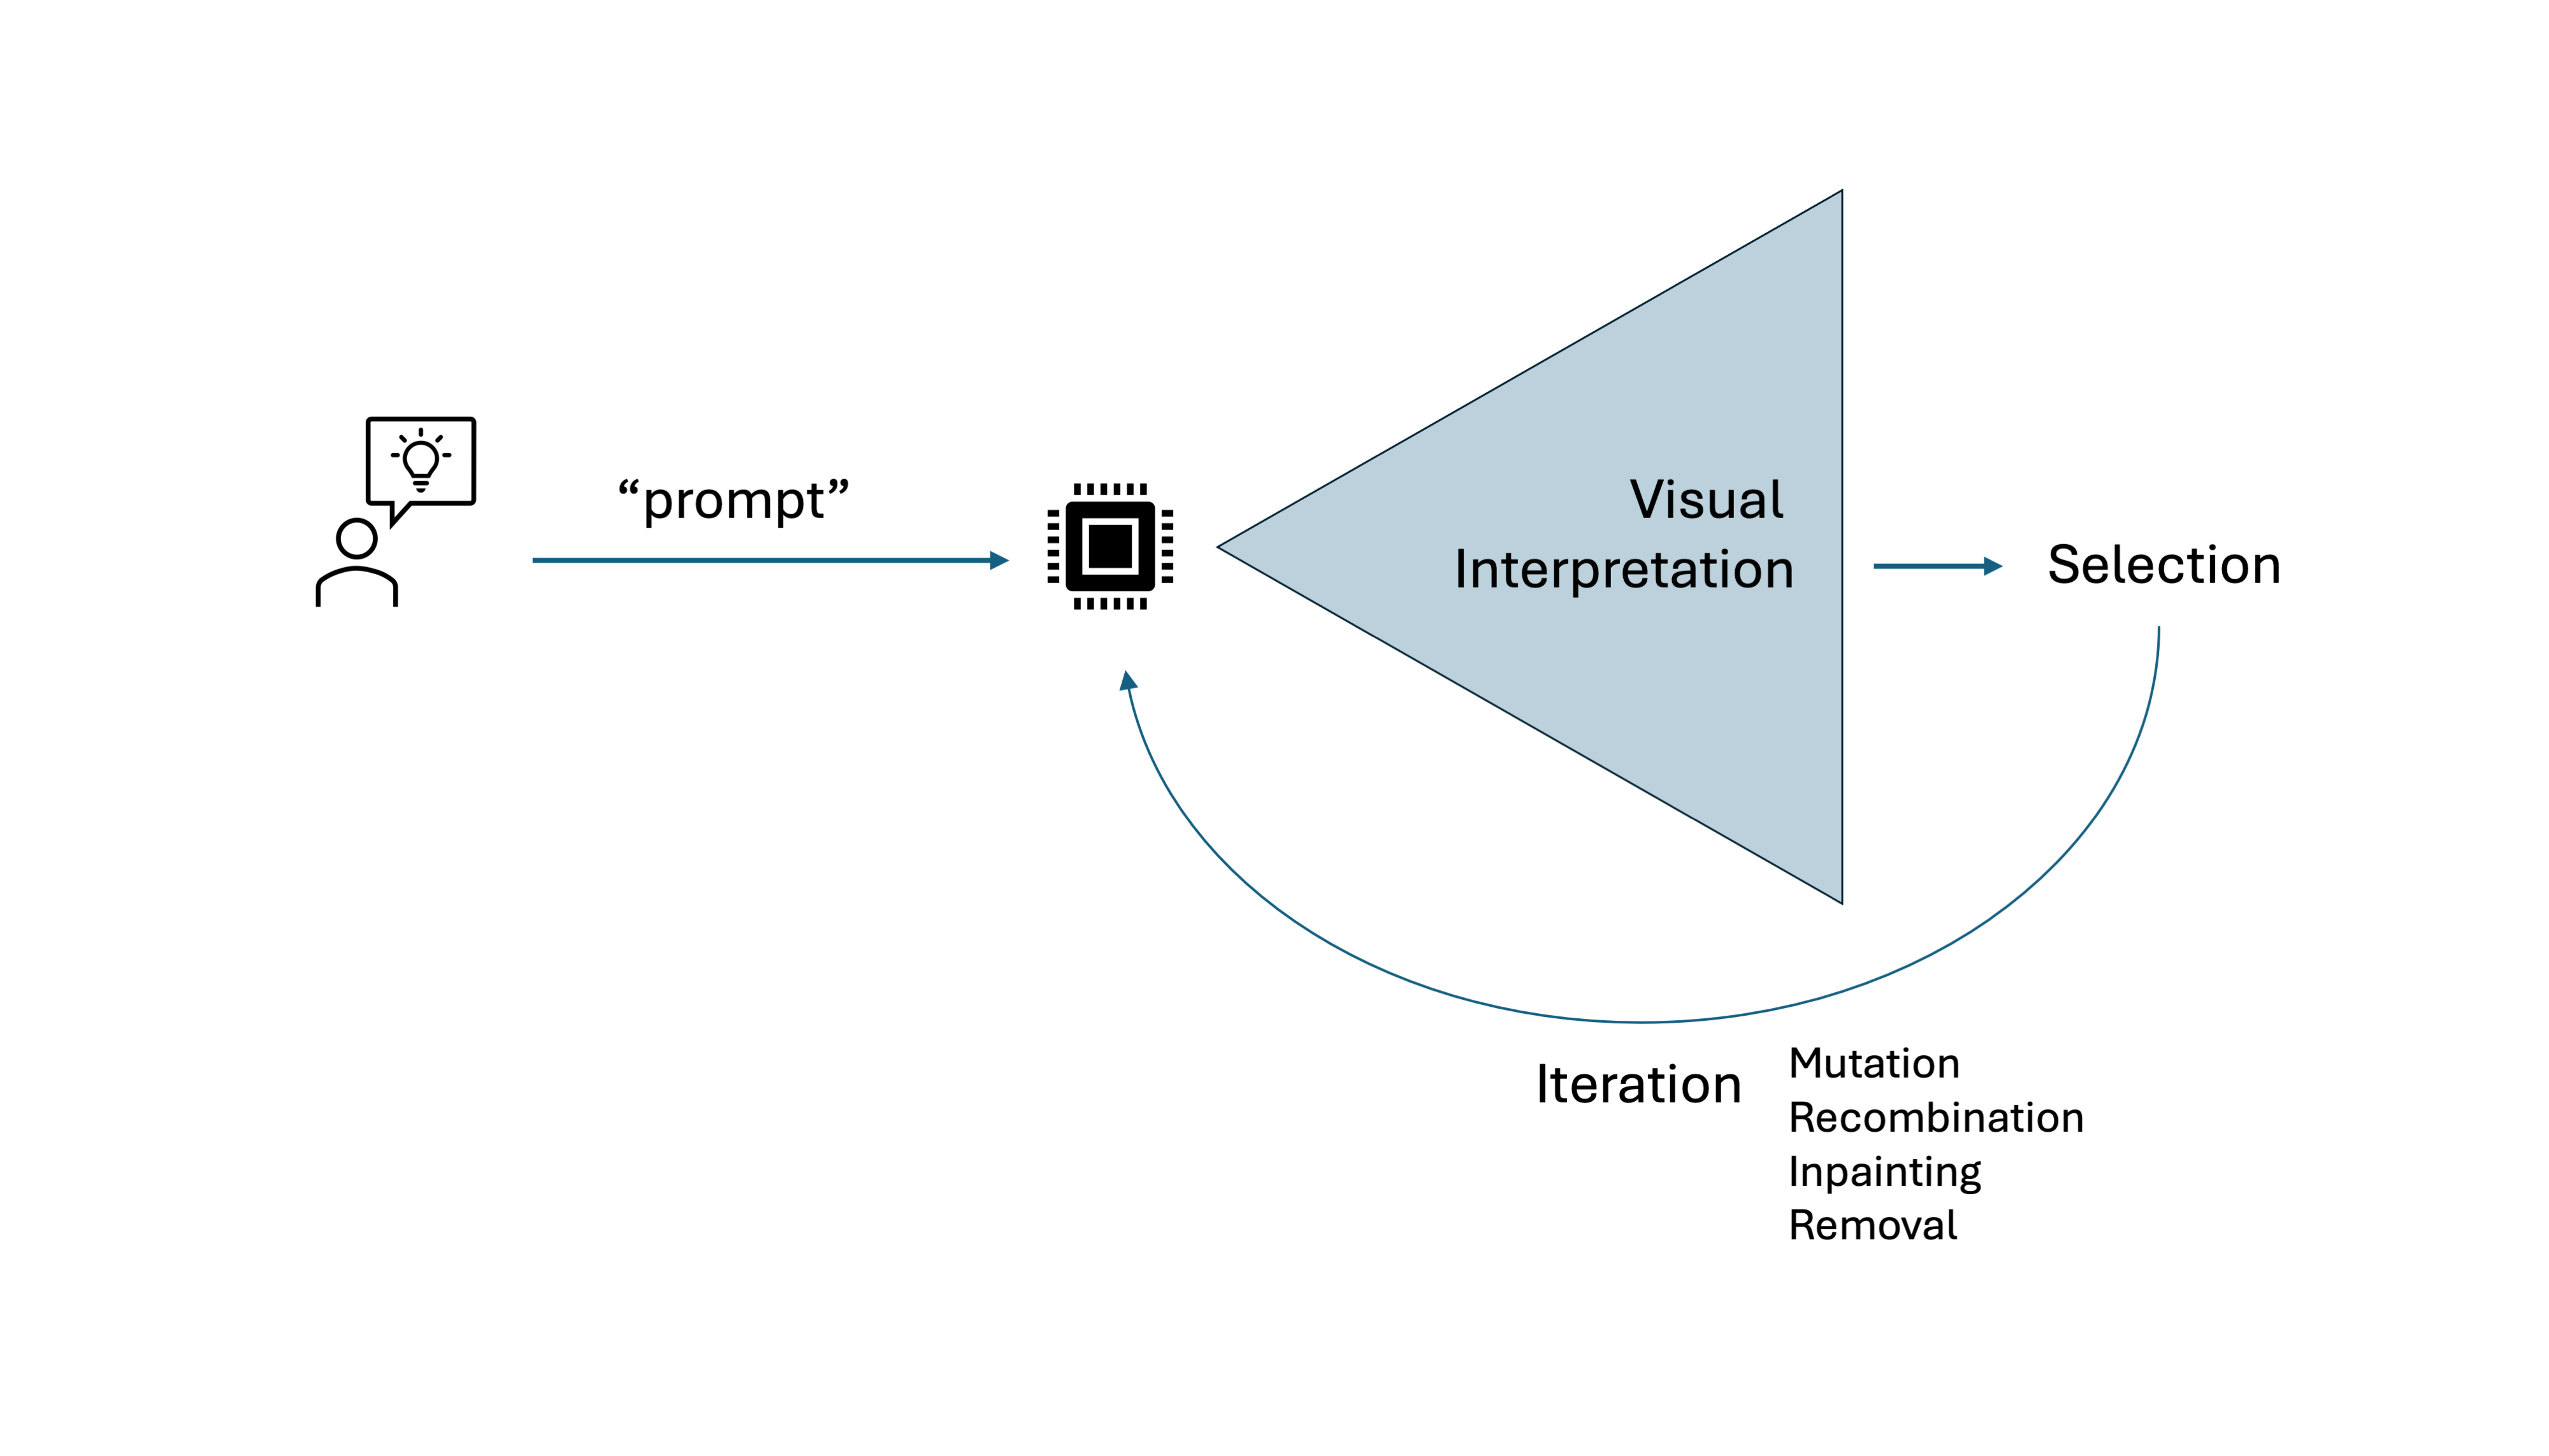
<p>When creating an illustration, it helps to use the generative AI tool as an interface to iterate over subsequent versions of the image <sup id="fnref:2" role="doc-noteref"><a href="#fn:2" class="footnote" rel="footnote">2</a></sup>. First, it can be used to generate a visual representation of the concept. Here, it can help to start from a sketch (“sketch-to-image”) or from an existing image (“mutation”).</p>

<p>Once a rough idea emerges, the image can be further refined. Areas can be erased (“removal”) and new elements can be added (“inpainting”). Multiple images parts can be combined and the junctions can be smoothed with further inpainting.</p>

<p>Finally, it often helps to correct minor errors manually. This can be done in a simple image editing software <sup id="fnref:3" role="doc-noteref"><a href="#fn:3" class="footnote" rel="footnote">3</a></sup>.</p>

<p><img src="/images/generative_ai/iterative_process.png" alt="Iterative process" title="Iterative process" /></p>

<p><img src="/images/generative_ai/combination_correction.png" alt="Combination of images" title="Correction through combination of images" /></p>

<p>Current generations of generative AI are still limited in their ability to generate images outside their training data. 
A few practical considerations are listed below:</p>

<h3 id="where-can-generative-ai-be-helpful"><em>Where can generative AI be helpful?</em></h3>

<p>Generative AI performs well for:</p>
<ul>
  <li>icons</li>
  <li>common objects/tools</li>
  <li>correcting parts of an image</li>
  <li>joining existing images</li>
  <li>generate variations of an existing image</li>
</ul>

<h3 id="where-will-generative-ai-fail"><em>Where will generative AI fail?</em></h3>

<p>Generative AI will fail for:</p>
<ul>
  <li>medical images: US, CT, MRI, Rx</li>
  <li>data representations: ECG, EEG</li>
  <li>uncommon objects/tools: BIS monitor, intra-cerebral pressure monitor</li>
  <li>anatomical structures</li>
  <li>lines/tubing</li>
</ul>

<p>Common generative AI models will generally fail when asked to create specific medical data representations. However, specific models exist for this aim <sup id="fnref:4" role="doc-noteref"><a href="#fn:4" class="footnote" rel="footnote">4</a></sup>.</p>

<h3 id="what-tool-to-use"><em>What tool to use?</em></h3>

<p>With the current pace of updates in the field, any list will be outdated in a few months. 
However, here are a few models that are currently popular:</p>
<ul>
  <li>Models: DALL-E (OpenAI), MidJourney (Midjourney, Inc.), Stable Diffusion (Stability AI)</li>
  <li>Image generation interface: <a href="https://www.bing.com/search?q=Bing+AI&amp;showconv=1&amp;FORM=hpcodx">Bing</a> (gives free access to DALL-E)</li>
  <li>Image modification interface: <a href="https://getimg.ai/image-editor">Getimg.ai</a> (gives access to Stable Diffusion inpainting and object removal, lots of free credits)</li>
  <li>Image variations interface: <a href="https://www.fotor.com/">Fotor</a></li>
</ul>

<h3 id="recommendations">Recommendations</h3>

<p>Practically:</p>
<ul>
  <li>Remain critical of generated images</li>
  <li>Correct generated images through inpainting / removal / image editing</li>
  <li>Check if journal allows publication of generated images</li>
  <li>Clearly state if an illustration was created with the help of AI tools</li>
  <li>Verify generated images are free of bias</li>
</ul>

<p><em>Full paper</em>: <a href="https://rdcu.be/dKt1E">Klug, J., Pietsch, U. Can artificial intelligence help for scientific illustration? Details matter. Crit Care 28, 196 (2024).</a></p>

<h3 id="references">References:</h3>

<div class="footnotes" role="doc-endnotes">
  <ol>
    <li id="fn:1" role="doc-endnote">
      <p>Guo X, Dong L, Hao D. RETRACTED: Cellular functions of spermatogonial stem cells in relation to JAK/STAT signaling pathway. Front Cell Dev Biol. 2024 Feb 13;11. <a href="#fnref:1" class="reversefootnote" role="doc-backlink">&#8617;</a></p>
    </li>
    <li id="fn:2" role="doc-endnote">
      <p>Thoring K, Huettemann S, Mueller RM. THE AUGMENTED DESIGNER: A RESEARCH AGENDA FOR GENERATIVE AI-ENABLED DESIGN. Proc Des Soc. 2023 Jul;3:3345–54. <a href="#fnref:2" class="reversefootnote" role="doc-backlink">&#8617;</a></p>
    </li>
    <li id="fn:3" role="doc-endnote">
      <p>The GIMP Development Team. GIMP. GIMP. Available from: https://www.gimp.org/ <a href="#fnref:3" class="reversefootnote" role="doc-backlink">&#8617;</a></p>
    </li>
    <li id="fn:4" role="doc-endnote">
      <p>Mendez M, Sundararaman S, Probyn L, Tyrrell PN. Approaches and Limitations of Machine Learning for Synthetic Ultrasound Generation. Journal of Ultrasound in Medicine. 2023;42(12):2695–706. <a href="#fnref:4" class="reversefootnote" role="doc-backlink">&#8617;</a></p>
    </li>
  </ol>
</div>]]></content><author><name>Julian Klug</name></author><category term="ICU" /><category term="AI" /><summary type="html"><![CDATA[Good illustrations are key for efficient scientific communication, education, and dissemination of knowledge. An image can easily convey complex concepts that are sometimes only cumbersomely captured in writing. In this light, more and more authors are making use of generative AI tools to create illustrations for their scientific publications.]]></summary></entry><entry><title type="html">ENRICH Trial Review - Trial of Early Minimally Invasive Removal of Intracerebral Hemorrhage</title><link href="https://www.julianklug.com/posts/ENRICH" rel="alternate" type="text/html" title="ENRICH Trial Review - Trial of Early Minimally Invasive Removal of Intracerebral Hemorrhage" /><published>2024-06-01T00:00:00+00:00</published><updated>2024-06-01T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/ENRICH</id><content type="html" xml:base="https://www.julianklug.com/posts/ENRICH"><![CDATA[<h3 id="clinical-question">Clinical question</h3>

<p>In patients with spontaneous intracerebral hemorrhage (ICH), does early minimally invasive surgical removal reduce the risk of death or severe disability as compared to medical management?</p>

<h3 id="pathophysiological-considerations">Pathophysiological considerations</h3>

<p><em>Hematoma expansion</em></p>
<ul>
  <li>Hematoma expansion is a major determinant of outcome in ICH</li>
  <li>Most hematoma expansion occurs within 3 hours of onset</li>
  <li>Hypertension is a major risk factor for hematoma expansion</li>
</ul>

<p><em>Edema and inflammation</em></p>
<ul>
  <li>secondary injury is driven by edema (both focal and global), inflammation and oxidative stress</li>
</ul>

<p><em>ICP elevation</em></p>
<ul>
  <li>both hematoma volume and edema contribute to ICP elevation</li>
</ul>

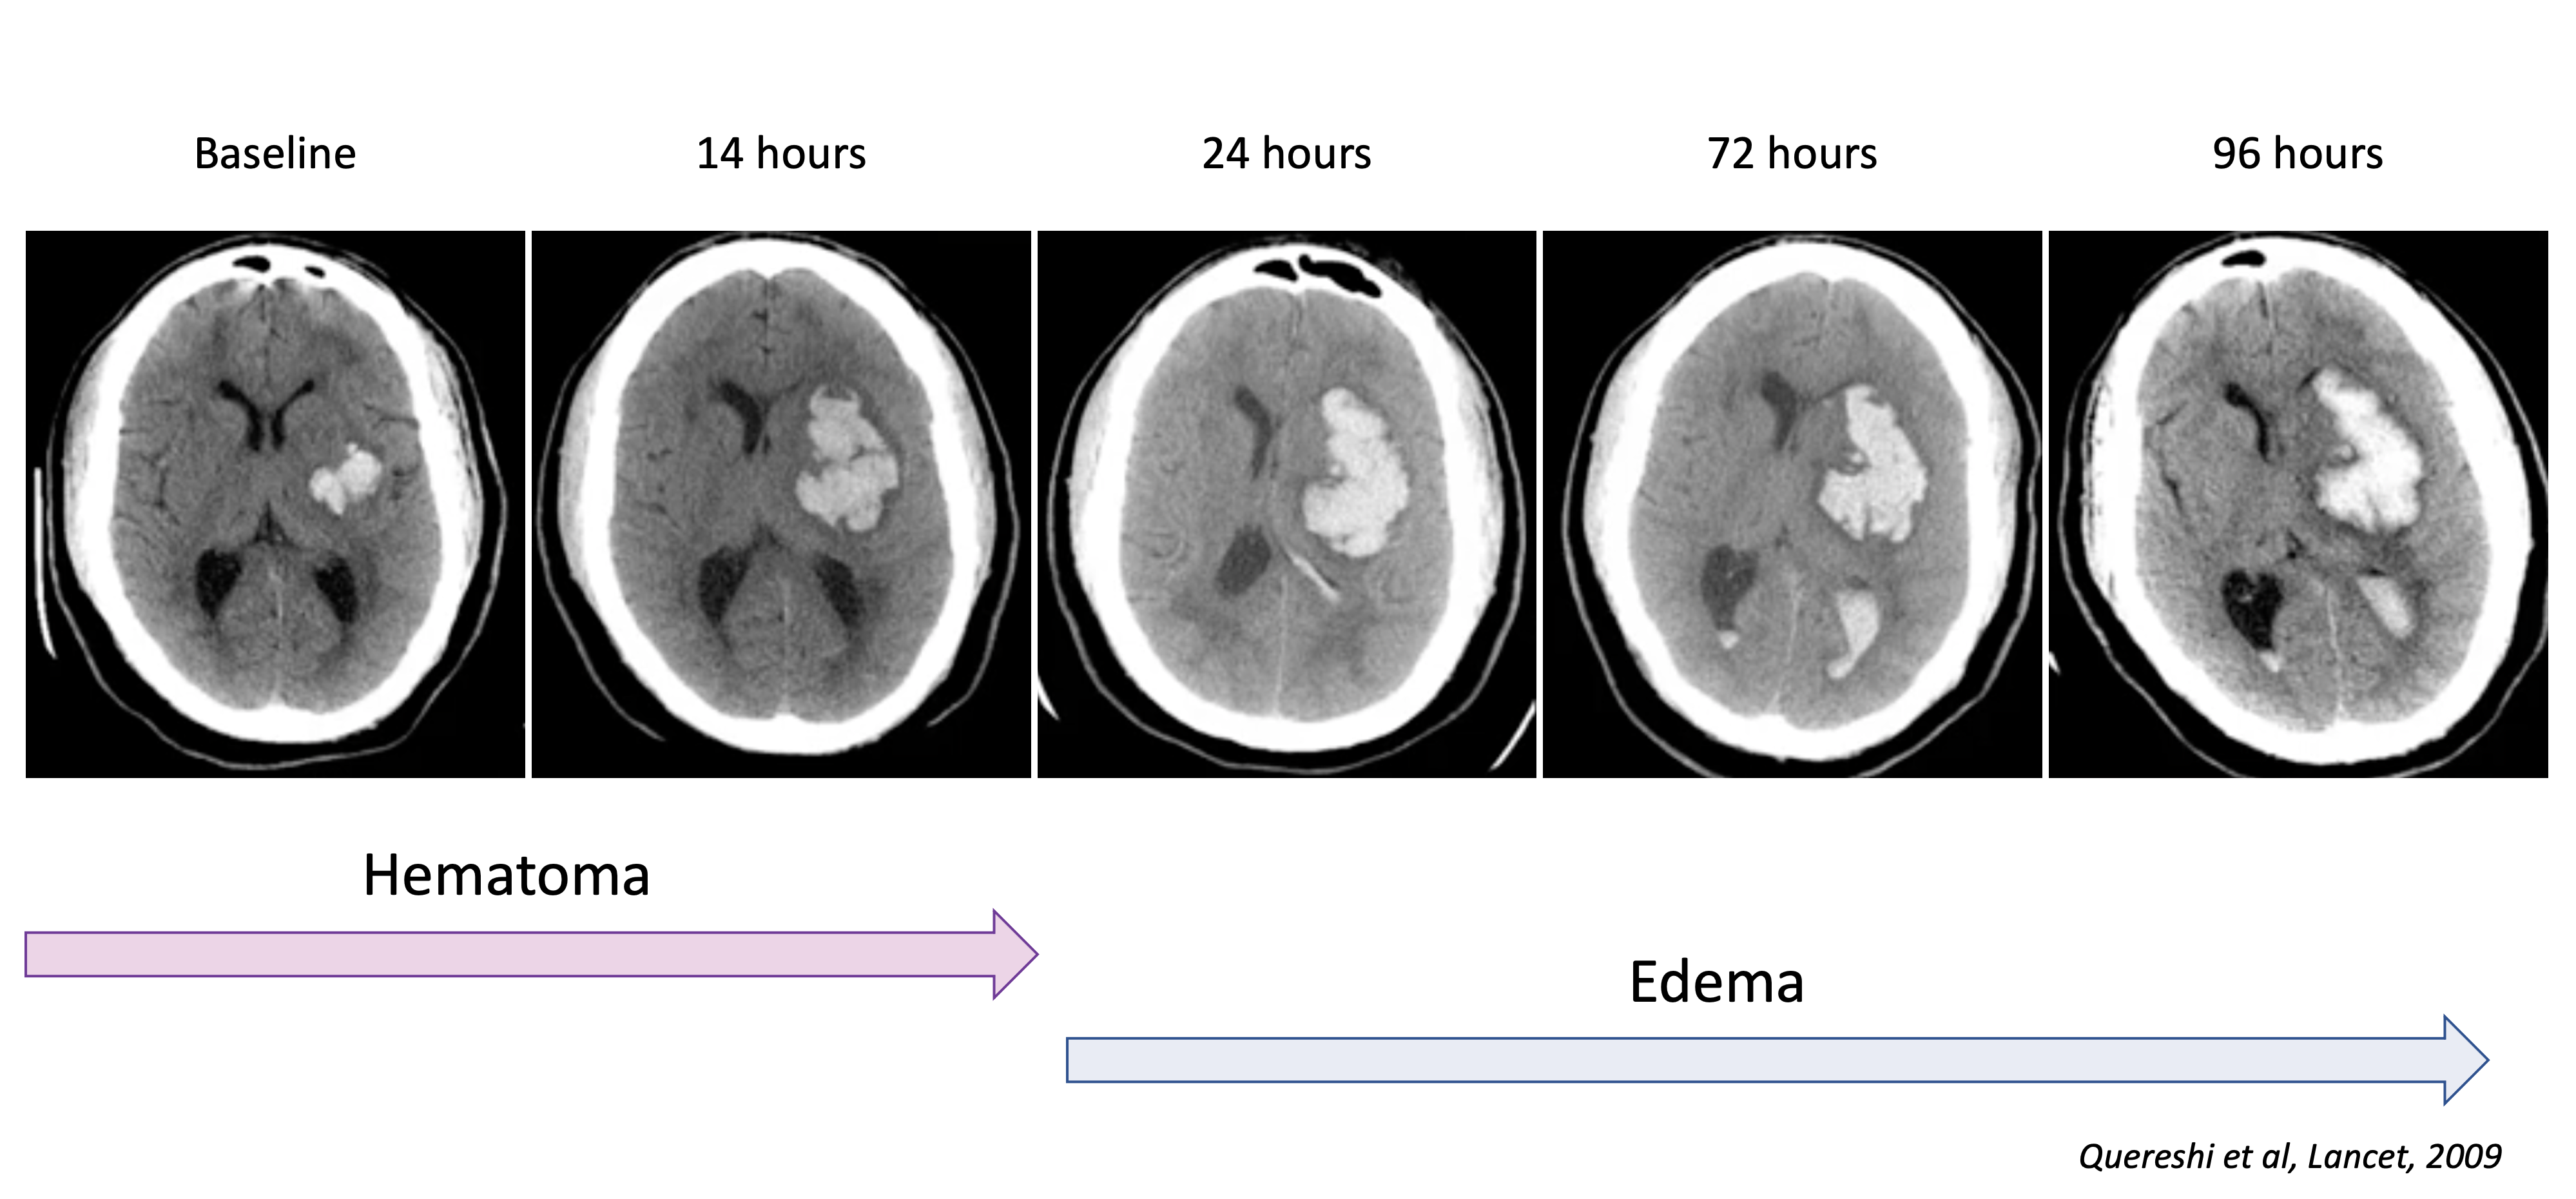
<p><img src="../images/INTERACT3_ICH/ICH_pathophysiology_timeline.png" alt="ICH pathophysiological timeline" /></p>

<h2 id="prior-evidence">Prior evidence</h2>

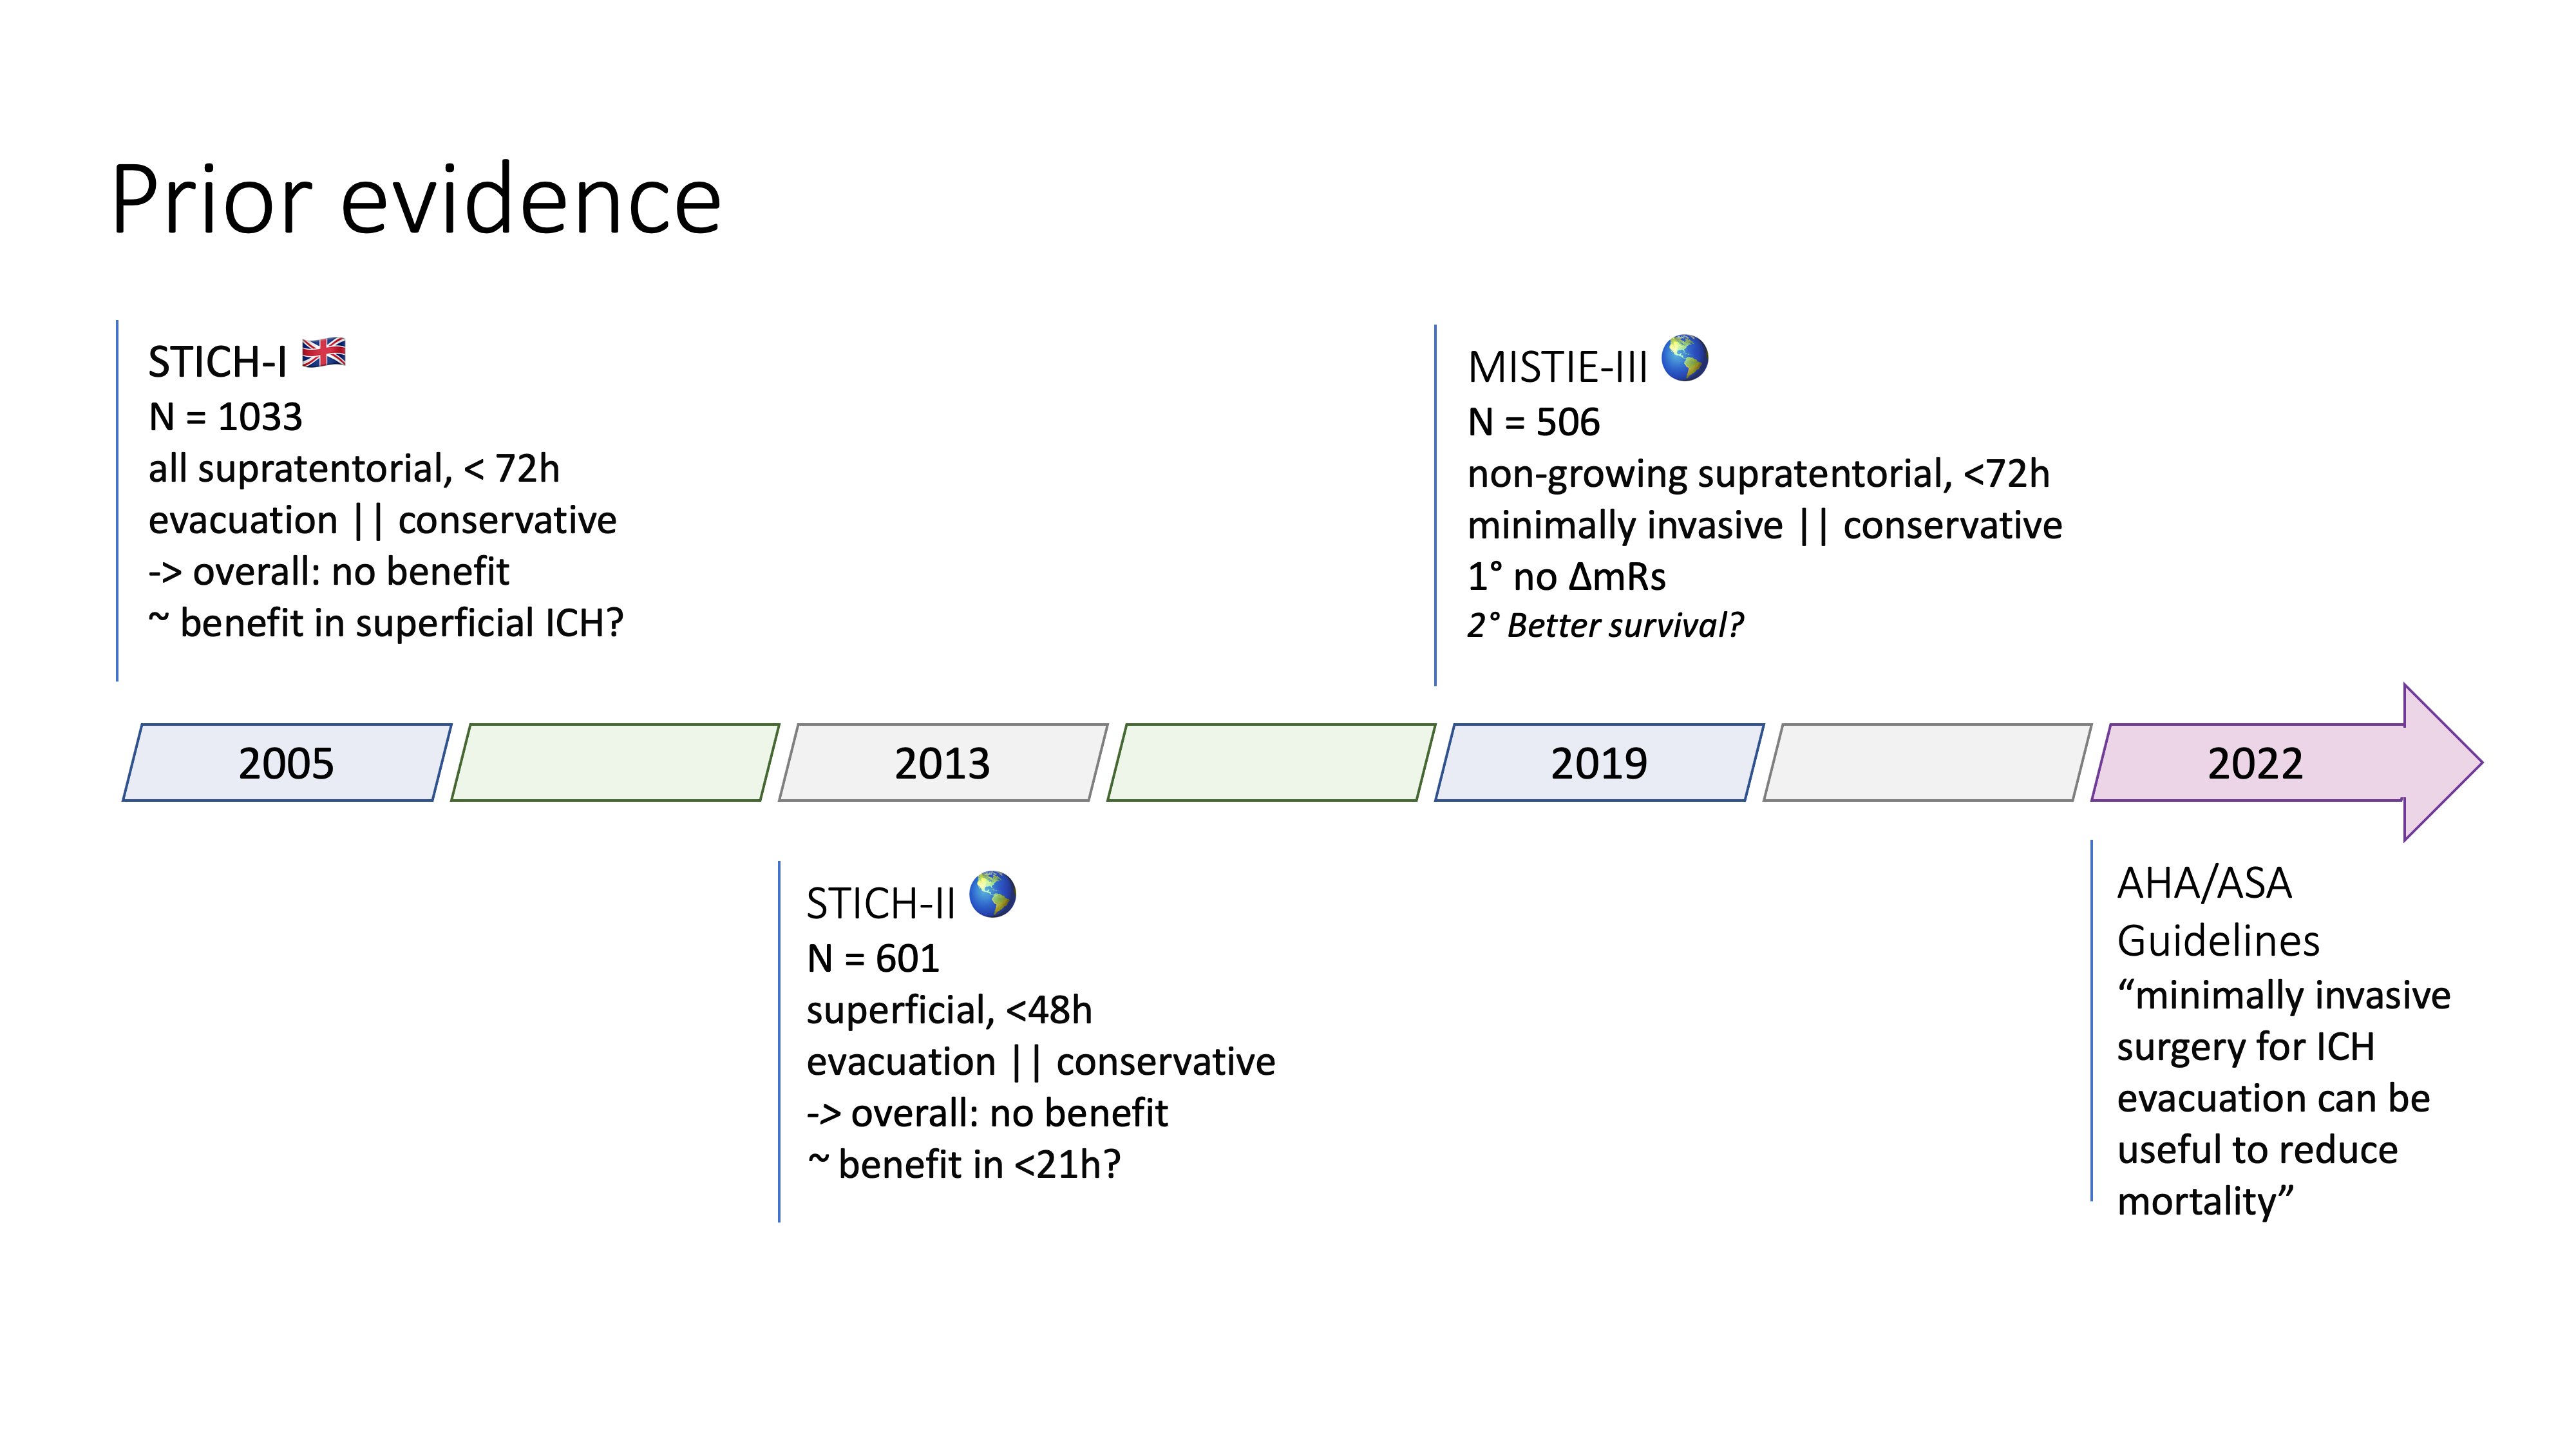
<p>Standard evacuation</p>
<ul>
  <li>STICH-I 2005 – n=1033 (UK), all supratentorial, &lt; 72h, evacuation vs. conservative, overall no benefit, potential benefit in superficial ICH (&lt; 1cm from surface)</li>
  <li>STICH-II 2013 – n=601 (Worldwide), superficial, &lt;48h, evacuation vs. conservative, overall no benefit, potential benefit in &lt;21h
    <ul>
      <li>max 100ml and no intraventricular hemorrhage</li>
    </ul>
  </li>
</ul>

<p>Minimal invasive evacuation</p>
<ul>
  <li>MISTIE-III, 2019 – n=506 (Worldwide), non-growing supratentorial, &lt;72h, minimally invasive vs. conservative, overall no benefit, potential survival benefit
    <ul>
      <li>acute bleeding excluded, insufficient clot evacuation</li>
    </ul>
  </li>
</ul>

<p>AHA 2022 guidelines</p>
<ul>
  <li>Class IIb recommendation for minimally invasive surgery for ICH evacuation for reduction of mortality</li>
</ul>

<p><img src="../images/ENRICH_ICH/ENRICH_prior_evidence.png" alt="ICH trials" /></p>

<p><em>Main critiques of prior trials:</em></p>
<ul>
  <li>early trials (STICH-I / II) too destructive</li>
  <li>interventions too late</li>
  <li>volume of evacuation too small</li>
</ul>

<h2 id="enrich-trial">ENRICH trial</h2>
<h3 id="population">Population</h3>

<p><em>Patient inclusion criteria</em></p>
<ul>
  <li>18-80y</li>
  <li>Spontaneous supratentorial ICH</li>
  <li>hematoma volume 30-80ml on CT</li>
  <li>GCS 5-14, NIHSS &gt; 5</li>
  <li>prior mRS 0-1</li>
  <li>surgery possible within 24h of las known well</li>
</ul>

<p><em>Patient exclusion criteria</em></p>
<ul>
  <li>long-term anticoagulation</li>
  <li>uncorrectable coagulopathy</li>
  <li><em>very poor or very good</em> neurological examination</li>
  <li>infratentorial &amp; thalamic ICH</li>
  <li>intraventricular hemorrhage &gt; 50% of lateral ventricle</li>
</ul>

<p>Screening: 
All ICH</p>

<p>Goal:</p>
<ul>
  <li>early intervention (&lt; 24h)</li>
  <li>active bleeding not an exclusion criteria</li>
</ul>

<h3 id="trial-design">Trial design</h3>

<p>Design: open label, parallel group, superiority randomized controlled adaptive trial</p>

<p>Period: 2016-2022
Location: US, 37 centers
Two subgroups: lobar and anterior basal ganglia</p>

<p>Randomisation: 1:1
Adaptive design:</p>
<ul>
  <li>interim analyis planned at 150, 175, 200, 225, 250, and 275 patients</li>
  <li>possible adaptive decisions: stop in either the anterior basal ganglia or the lobar location, stop for all, or continue for all</li>
</ul>

<h3 id="intervention">Intervention</h3>

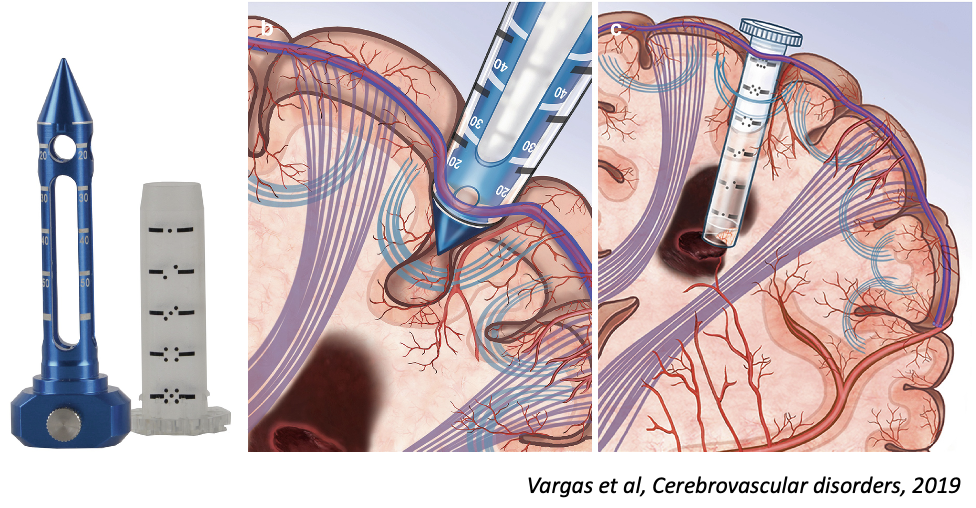
<p>craniotomy, imaging-guided trajectory w/ BrainPath port, Suction evacuation</p>

<p>Comments:</p>
<ul>
  <li>planning for white matter tract preservation (Software by Nico corporation)</li>
</ul>

<p><img src="../images/ENRICH_ICH/nico_brainport.png" alt="Brainport" /></p>

<h3 id="outcomes">Outcomes</h3>

<p><em>Primary outcome</em>: utility-weighted modified Rankin Scale (mRS) at 6 months</p>

<p><em>Main secondary outcomes</em>:</p>
<ul>
  <li>significant post-operative rebleeding (&gt;+ 4 pts on NIHSS or -2pts on GCS)</li>
  <li>Length of stay</li>
  <li>mRS at 7 days / discharge / 30 days / 90 days</li>
  <li>survival at 6 months</li>
</ul>

<p><em>Safety Outcomes</em>:</p>
<ul>
  <li>death at 30 days</li>
  <li>change in hematoma volume</li>
</ul>

<p><em>Assessment</em>:</p>
<ul>
  <li>audio-recorded structured interview at 30, 90, and 180 days</li>
  <li>assessment of outcome by blinded neuropsychologist</li>
</ul>

<p><img src="..%2Fimages%2FINTERACT3_ICH%2Fmrs_distribution.png" alt="mrs_distribution.png" /></p>

<h3 id="results">Results</h3>
<h4 id="trial-conduct">Trial conduct</h4>

<p><em>Recruitment:</em> 37 sites, 300 patients, 6 years</p>
<ul>
  <li>highly selected population, <strong><em>only 2.5%</em></strong> of screened patients included</li>
  <li>lost to follow-up: 5%</li>
</ul>

<p>Adaptation triggerred: After 175 patients, the trial was stopped for the anterior basal ganglia location</p>

<p><em>Population:</em></p>
<ul>
  <li>globally well-balanced among groups</li>
  <li>representative of Western ICH population</li>
  <li>only 20% of prior mRS =&lt; 1 ?? (seems like an error in Table 1, as the inclusion criteria was mRS 0-1)</li>
</ul>

<p><em>Intervention:</em></p>
<ul>
  <li>median time to surgery: 16.7h</li>
  <li>remaining hematoma volume: 15ml</li>
</ul>

<h4 id="outcomes-1">Outcomes</h4>

<p><em>Primary outcome</em>: significant difference in utility weighted mRS at 6 months (0.45 vs 0.37, posterior probability of superiority 0.98)</p>
<ul>
  <li>mainly driven by the lobar subgroup (0.51 vs 0.37)</li>
  <li>no effect in the anterior basal ganglia subgroup (0.34 vs 0.37)</li>
</ul>

<p><em>Secondary outcomes</em>:</p>
<ul>
  <li>Distribution of mRs shift: evenly distributed over all categories (not only increase in survival)</li>
  <li>globally all secondary outcomes were in favor of the intervention, notably:
    <ul>
      <li>reduced ICU and hospital length of stay</li>
      <li>reduced time on the ventilator</li>
      <li>less salvage craniectomy (3% vs 20%)</li>
    </ul>
  </li>
  <li>Difference in mRs =&lt; 3 and mortality with numerical benefit for intervention, but not significant
    <ul>
      <li>this could be mainly driven by a lack of power (trial was designed to detect change of overall shift, not individual categories of mRS)</li>
    </ul>
  </li>
</ul>

<p><em>Subgroups</em>:</p>
<ul>
  <li>Main benefit in: patients &gt;= 65y, lobar location, GCS 9-14 (and more benefit in women?)</li>
</ul>

<p><em>Safety outcomes</em>:</p>
<ul>
  <li>globally less adverse events in the intervention group</li>
  <li>notably fewer pneumonia (although number of respiratory failure events was similar), less cerebral edema and less secondary ICH</li>
</ul>

<h3 id="assessment">Assessment</h3>

<p><em>Weaknesses</em></p>
<ul>
  <li>Highly selected population: only 2.5% of screened patients included (this was confirmed by recent feasibility exploration in Sweden<sup id="fnref:2" role="doc-noteref"><a href="#fn:2" class="footnote" rel="footnote">1</a></sup>)</li>
  <li>Single technique: other minimally invasive techniques were not explored (SCUBA endoscopic techniques are also currently developed)
    <ul>
      <li>Not clear if the benefit is from the instruments or the guidance provided by the software</li>
      <li>The trial was sponsored by Nico corporation - although no interference was reported, the potential for bias is present</li>
    </ul>
  </li>
  <li>Generalisation outside US? although the authors show that a variety of centers were included (and the brain port could be mimicked by a 50cc seringue), the generalisation to other countries is not clear</li>
  <li>«minimally» invasive: the brain port is still of significant size</li>
  <li>Primary bayesian analysis, making interpretation and back-checking of statistics more difficult
    <ul>
      <li>design and statistics was outsourced to a statistics company</li>
    </ul>
  </li>
  <li>Medium size trial (300 patients)</li>
</ul>

<p></p>
<p><em>Strengths</em></p>
<ul>
  <li>First ever positive trial for supratentorial ICH</li>
  <li>Extremely well-designed RCT</li>
  <li>Blinding was done as much as possible</li>
</ul>

<p><em>Interpretation</em></p>
<ul>
  <li>effect on outcomes is clinically significant (seems to be not only driven by survival at the expense of severe disability)</li>
  <li>the benefit is mainly driven by the lobar subgroup</li>
  <li>in the anterior basal ganglia subgroup, no conclusion can be drawn</li>
</ul>

<p><em>Bottomline</em>: 
In patients with lobar ICH, minimally invasive surgery within 24h of onset improves outcome at 6 months.</p>

<p><em>Open questions</em>:</p>
<ul>
  <li>is the benefit driven by the planning software or the technique?</li>
  <li>is this small population worth the investment in the technique?</li>
</ul>

<h3 id="adapted-algorithm-and-state-of-the-evidence">Adapted algorithm and state of the evidence</h3>

<p><img src="../images/ENRICH_ICH/updated_ICH_algorithm.png" alt="ICH algorithm" /></p>

<p><img src="../images/ENRICH_ICH/ICH_state_of_evidence.png" alt="ICH evidence" /></p>

<h3 id="references">References:</h3>

<div class="footnotes" role="doc-endnotes">
  <ol>
    <li id="fn:2" role="doc-endnote">
      <p>Apostolaki-Hansson T, Hillal A, Göransson N, Hansen BM, Norrving B, Ramgren B, et al. The potential for minimally invasive intracerebral hemorrhage evacuation in routine healthcare: applicability of the ENRICH trial criteria to an unselected cohort. Front Stroke. 2024 May 17;3. <a href="#fnref:2" class="reversefootnote" role="doc-backlink">&#8617;</a></p>
    </li>
  </ol>
</div>]]></content><author><name>Julian Klug</name></author><category term="ICU" /><category term="Neurocritical care" /><summary type="html"><![CDATA[Clinical question]]></summary></entry><entry><title type="html">INTERACT3 Review - Care Bundle with Blood Pressure Reduction in Acute Cerebral Haemorrhage Trial</title><link href="https://www.julianklug.com/posts/INTERACT3" rel="alternate" type="text/html" title="INTERACT3 Review - Care Bundle with Blood Pressure Reduction in Acute Cerebral Haemorrhage Trial" /><published>2023-09-10T00:00:00+00:00</published><updated>2023-09-10T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/INTERACT3</id><content type="html" xml:base="https://www.julianklug.com/posts/INTERACT3"><![CDATA[<h3 id="clinical-question">Clinical question</h3>

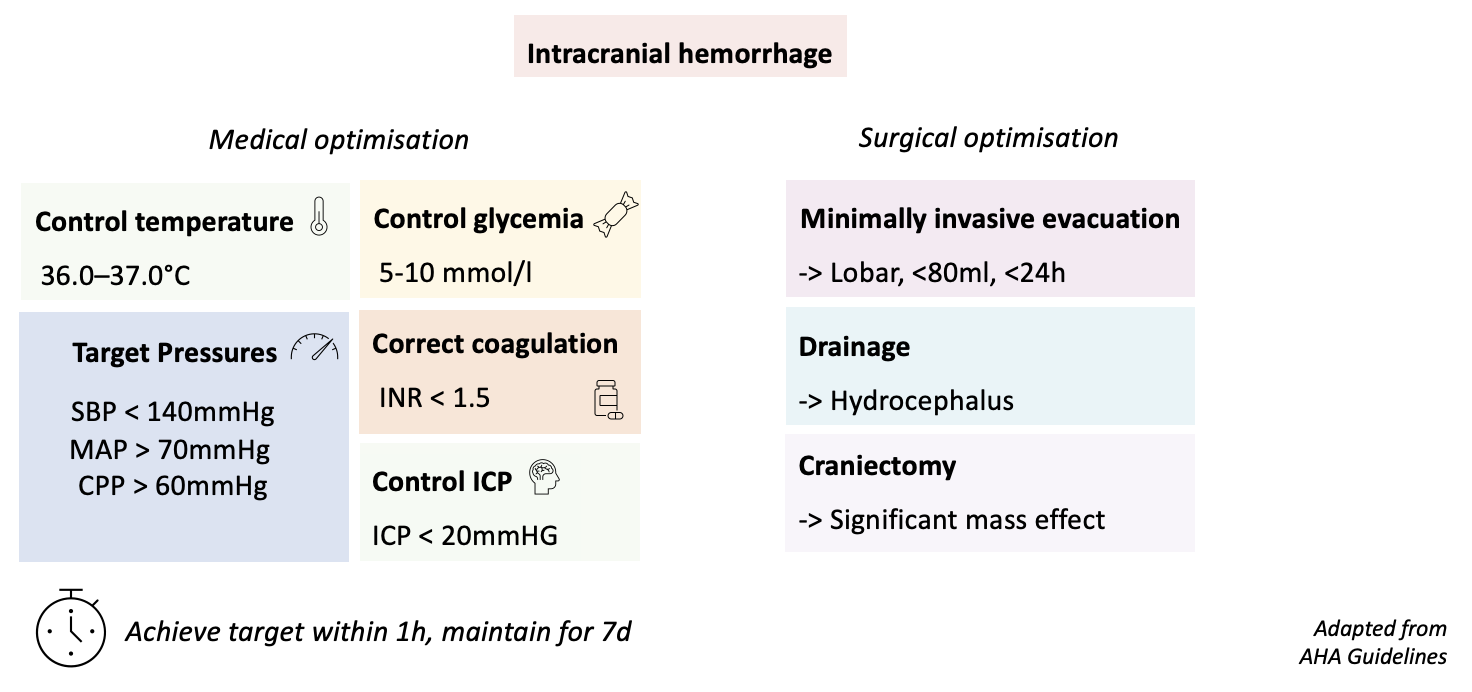
<p>In patients with spontaneous intracerebral hemorrhage (ICH), does a bundle of intensive blood pressure lowering (target systolic BP &lt;140 mm Hg within 1 hour), protocolized glucose and temperature control as well as reversal of anticoagulation reduce the risk of death or severe disability as compared to non protocolized standard of care?</p>

<p><em>This article will mainly focus on the blood pressure lowering aspect of the trial.</em></p>

<h3 id="pathophysiological-considerations">Pathophysiological considerations</h3>

<p>The early hours after ICH are characterized by balance act between hematoma expansion and maintaining cerebral perfusion.</p>

<p><em>Hematoma expansion</em></p>
<ul>
  <li>Hematoma expansion is a major determinant of outcome in ICH</li>
  <li>Most hematoma expansion occurs within 3 hours of onset</li>
  <li>Hypertension is a major risk factor for hematoma expansion</li>
</ul>

<p><em>Acute hypertensive response</em></p>
<ul>
  <li>Hypertension is frequently observed in the acute phase of ICH</li>
  <li>Hypertension could be a autoregulatory response to maintain cerebral perfusion</li>
  <li>Peri-hematoma penumbra seems to be a myth, as perihematomal tissue as proportionally reduced metabolism and perfusion</li>
</ul>

<p>The later stages seem to be driven by secondary injury, such as edema (both focal and global), inflammation and oxidative stress.</p>

<p><img src="../images/INTERACT3_ICH/ICH_pathophysiology_timeline.png" alt="ICH pathophysiological timeline" /></p>

<h2 id="prior-evidence">Prior evidence</h2>

<p><em>RCTs</em></p>
<ul>
  <li>INTERACT1 2008 – n=404, &lt;140 vs &lt;180mmHg, BP goals barely met, possibly less hematoma growth</li>
  <li>ATACH1 2010 – n=60 IV anti-hypertensive, BP goals achieved</li>
  <li>INTERACT2 2013 – n=2839, BP goals barely met, no diff in hematoma expansion, no diff in primary (mrs &gt;3), tendancy toward better mrs</li>
  <li>ATACH2 2016 – n=1000 (stopped for futility), BP goals achieved, trend toward reduced hematoma expansion, no diff in outcome, more AKI</li>
  <li>AHA/ASA guidelines 2022: lowering systolic BP (SBP) to a target range of 130 to 140 mmHg is safe and may be reasonable</li>
</ul>

<p><img src="..%2Fimages%2FINTERACT3_ICH%2FICH_RCT_timeline.png" alt="ICH RCT timeline" /></p>

<p><em>Bundle trials</em></p>
<ul>
  <li>Quality in Acute Stroke Care trial 2011 – n=1696 (hemorrhagic &amp; ischemic), pre/post analysis, large mortality benefit (-16%)
    <ul>
      <li>Bundle: management of fever / hyperglycemia / swallowing</li>
    </ul>
  </li>
  <li>ICH ABC Bundle 2019 – n= 973, pre/post analysis, UK, large mortality benefit (-11%)
    <ul>
      <li>Bundle: Anticoagulation reversal, &lt;140mmHg, referral to NCH</li>
    </ul>
  </li>
</ul>

<p><img src="..%2Fimages%2FINTERACT3_ICH%2FICH_bundle_timeline.png" alt="ICH_bundle_timeline.png" /></p>

<p><em>Main critiques of prior trials:</em></p>
<ul>
  <li>Achieved BP goals differed between trials (INTERACT2: 140mmHg, ATACH2: 110mmHg)</li>
  <li>Outcome should be assessed at 6 months, not 3 months (as traditionally done in stroke trials)</li>
</ul>

<p><em>Gist:</em> Meta-analyses found an overall benefit (shift in ordinal mRS scale) of intensive BP lowering in ICH and guidelines started mentioning / recommending a target of 130-140mmHg.</p>

<h2 id="interact3">INTERACT3</h2>
<h3 id="population">Population</h3>

<p><em>Site inclusion criteria</em></p>
<ul>
  <li>No existing protocol for BP lowering</li>
  <li>Local champion</li>
</ul>

<p><em>Patient inclusion criteria</em></p>
<ul>
  <li>&gt; 18y</li>
  <li>Spontaneous ICH, confirmed by CT</li>
  <li>≤ 6 hours from onset</li>
</ul>

<p><em>Patient exclusion criteria</em></p>
<ul>
  <li>Evidence that ICH is secondary to AVM / aneurysm / trauma / ichemic stroke / lysis</li>
  <li>High likelihood that patient will not adhere to treatment / follow-up</li>
</ul>

<p>Screening: continuous of all arriving patients (controlled by trial staff)</p>

<p>Participating countries: Brazil, China, India, Mexico, Nigeria, Pakistan, Peru, Sri Lanka, Viet Nam, Chile</p>

<p><em>Why?</em></p>
<ul>
  <li>Probably no equipoise in high-income countries or existing protocols</li>
  <li>High &amp; rising prevalence of hypertension and ICH in LMICs</li>
  <li>Trial powered by the George Institute, realising large studies, targeting global health issues (with an established trial network)</li>
</ul>

<h3 id="trial-design">Trial design</h3>

<p>Stepped wedge cluster randomized trial: each sites starts with standard of care, then switches to intervention at after a certain number of periods (1-3), as allocated by site-level randomisation.</p>

<p>Period: 3-4 months, or until a certain (variable) number of patients were enrolled</p>

<p><em>Comments:</em></p>
<ul>
  <li><em>highly variable period lengths between clusters</em></li>
  <li>COVID pandemic fell in middle, with stopped recruitement in some countries -&gt; later phases were extended</li>
  <li>Advantages: allows for fast intervention (no need to wait for patient to be randomized), and testing implementation of protocol</li>
</ul>

<p><img src="..%2Fimages%2FINTERACT3_ICH%2FINTERACT3_trial_design.png" alt="INTERACT3_trial_design.png" /></p>

<h3 id="intervention">Intervention</h3>

<p><em>Bundle</em></p>
<ul>
  <li>Target SBP 130-140mmHg</li>
  <li>Target INR &lt; 1.5</li>
  <li>Glucose control
    <ul>
      <li>Non-diabetic: 6.1-7.8 mM</li>
      <li>Diabetic: 7.8-10.0 mM</li>
      <li><em>Comment:</em> very tight range, lower than NICE-SUGAR (&lt;10) &amp; Quality in acute stroke care (&lt; 11), higher than Leuven trials (4.4-6.1)</li>
    </ul>
  </li>
  <li>Temperature control: &lt; 37.5°C</li>
</ul>

<p>Targets were to be achieved within 1h, and maintained for 7d.</p>

<p><em>Protocol implementation</em></p>
<ul>
  <li>Before intervention: 7-10d online training</li>
  <li>During intervention:
    <ul>
      <li>Center specific protocol (targeted to available drugs)</li>
      <li>Monitoring of SBP / INR / glycemia / temperature (trial staff)</li>
      <li>Monthly feedback</li>
      <li>2 QI Meetings</li>
    </ul>
  </li>
</ul>

<h3 id="outcomes">Outcomes</h3>

<p><em>Primary outcome</em>: ordinal shift on modified Rankin Scale (mRS) at 6 months</p>

<p><em>Main secondary outcomes</em>: mRS ≤ 2 vs ≥ 3, mortality, quality of life, residence</p>

<p><em>Safety Outcomes</em>: serious adverse events (self reported, only if life-threatening / disability / or triggering readmission / prolongation)</p>

<p><em>Assessment</em>: by phone by “blinded” personnel (central office only in China / Chile / Brazil / Nigeria) - otherwise located at hospitals (who probably knew the current protocol being applied)</p>

<p><img src="..%2Fimages%2FINTERACT3_ICH%2Fmrs_distribution.png" alt="mrs_distribution.png" /></p>

<h3 id="results">Results</h3>
<h4 id="trial-conduct">Trial conduct</h4>

<p><em>Recruitment:</em> 121 sites, 7036 patients randomized</p>
<ul>
  <li>30% patients excluded upon screening, but adequate reasons (mostly presentation &gt; 6h, no consent, structural cause)</li>
  <li>Minimum 8% lost to follow-up &amp; 11% with no primary outcome data</li>
  <li>–&gt; Slightly underpowered (planned for 90% power: 110sites, 8360 patients)</li>
</ul>

<p><em>Population:</em> Randomisation worked, well-balanced between groups</p>
<ul>
  <li>at baseline: compared to Swiss ICH patients, these patients tended to be ~10y younger (62y), fitter (77% pre-mRS 0), and with less AF / D2 / coronary disease, but similar level of hypertension</li>
  <li>at presentation: TAS 175 mmHg, moderately severe neuro deficit (NIHSS 13), GCS 12
    <ul>
      <li>Only very few with altered T° / INR (&lt;2%)</li>
    </ul>
  </li>
</ul>

<p><em>Intervention (BP):</em> Small but significant difference in SBP between groups</p>
<ul>
  <li>on average: target achieved at 4h vs 8h</li>
  <li>at 1h: 150 vs 160mmHg</li>
  <li>Main agents used
    <ul>
      <li>IV: urapidil (60%), nicardipine (8.5%), sodium nitroprusside, labetalol, nimodipine, very little clevidipine (~2%)</li>
      <li>PO: ACEi (~60%), CCB (~76%)</li>
    </ul>
  </li>
  <li>Compared to prior trials:
    <ul>
      <li>Less intensive than ATACH2 (which had shown an increase in AKI)</li>
      <li>More than INTERACT2</li>
    </ul>
  </li>
</ul>

<p><img src="..%2Fimages%2FINTERACT3_ICH%2FINTERACT3_BP_trajectories.png" alt="INTERACT3_BP_trajectories.png" /></p>

<p><em>Intervention (rest of bundle)</em>: no significant separation between groups</p>

<h4 id="outcomes-1">Outcomes</h4>

<p><em>Primary outcome</em>: favorable shift in mRS in intervention group (OR 0.86; 95% CI 0.76-0.97, p=0.015), consistent across all adjustments/calculations</p>
<ul>
  <li>Statistical calculation of primary outcome had to be changed post-protocol. Initially it was planned to adjust for time passing by correcting for (= using as fixed factor) period, however as the period length varied a lot, this resulted in a non-significant primary outcome (probably because of correlation between intervention assignment and period). The authors changed this to correcting for time by using calendar time periods. To a statistical novice, this seems to be okay.</li>
  <li>Size in shift in primary outcome not very impressive, with notably less mRs 0 &amp; more mRs 3?</li>
</ul>

<p><em>Secondary outcomes</em>: all strictly non-significant, but trends consistent with primary outcome</p>
<ul>
  <li>notably adjusted risk of death 11% vs 14% (not significant)</li>
</ul>

<p><em>Subgroups</em>: trends consistent across subgroups, no clear effect modifiers</p>

<p><em>Safety outcomes</em>: reported reduced adverse events</p>
<ul>
  <li>gross prevalence seems under-reported (ex pneumonia prevalence after ICH should be 10-60%)</li>
  <li>a reduction in probably unrelated adverse events is reported (e.g. gastro-intestinal disorders)</li>
  <li>no diff. in AKI, but probably underreported as this was not systematically assessed</li>
</ul>

<p><em>Other:</em> no difference in hematoma expansion</p>

<h3 id="assessment">Assessment</h3>

<p><em>Weaknesses</em></p>
<ul>
  <li>Small effect in primary outcome</li>
  <li>Generalizability? Mostly China &amp; LMICs, patients with no anti-coagulation</li>
  <li>Not fully blinded (outcome assessment was probably not blinded in some sites)</li>
  <li>Outcome assessment by phone</li>
  <li>Bundle: Although BP was most prominent aspect, effect of other interventions cannot be excluded</li>
  <li>Hawthorne effect: sites were aware of being in a trial, and were probably more attentive to patient care when in the bundle phase</li>
  <li>Renal side effects not systematically assessed</li>
</ul>

<p></p>
<p><em>Strengths</em></p>
<ul>
  <li>Large international, well conducted RCT</li>
  <li>Pragmatic bundle, large scale implementation</li>
  <li>Relevant global health issue</li>
</ul>

<p><em>Interpretation</em></p>
<ul>
  <li>Bayesian: given a probable a priori beneficial effect of BP lowering, this trial provides further evidence for a beneficial effect of intensive BP lowering in ICH</li>
  <li>Probably an absolute small effect (~-2-3% mortality), but applied on large scale</li>
  <li>Implementation of a bundle/guideline should be recommended, as it carries further benefits
    <ul>
      <li>organising care &amp; promoting monitoring</li>
      <li>defining goals &amp; interventions renders a disease without hope more manageable, and thus probably improves care</li>
      <li>highlights urgency of hemorrhagic stroke - time is brain</li>
    </ul>
  </li>
  <li>Exact mechanism of benefit of BP lowering is still unclear (no diff. in hematoma expansion)</li>
</ul>

<p><em>Bottomline</em>: Bundle of intensive BP lowering (target 130-140mmHg), glucose &amp; temperature control, and reversal of anticoagulation in ICH patients improves outcomes.</p>

<h3 id="adapted-algorithm-for-ich-management">Adapted algorithm for ICH management</h3>

<p><img src="..%2Fimages%2FINTERACT3_ICH%2FICH_Algorithm.png" alt="ICH Algorithm" /></p>

<h3 id="references">References:</h3>

<ol>
  <li>
    <p>Greenberg, S. M. et al. 2022 Guideline  for  the  Management  of  Patients  With  Spontaneous  Intracerebral  Hemorrhage: A Guideline  From  the American Heart  Association/American Stroke  Association. Stroke 53, e282–e361 (2022).</p>
  </li>
  <li>
    <p>Qureshi, A. I. Acute  Hypertensive  Response  in  Patients  With  Stroke. Circulation 118, 176–187 (2008).</p>
  </li>
  <li>
    <p>Parry-Jones, A. R. et al. An  Intracerebral  Hemorrhage Care Bundle  Is  Associated  with  Lower  Case  Fatality. Ann  Neurol 86, 495–503 (2019).</p>
  </li>
  <li>
    <p>Investigators, A. T. of A. C. H. (ATACH). Antihypertensive  treatment  of  acute  cerebral  hemorrhage*. Critical Care Medicine 38, 637 (2010).</p>
  </li>
  <li>
    <p>Moullaali, T. J. et al. Blood  pressure  control  and  clinical  outcomes  in  acute  intracerebral  haemorrhage: a preplanned  pooled  analysis  of  individual  participant data. The  Lancet  Neurology 18, 857–864 (2019).</p>
  </li>
  <li>
    <p>Yu, K., Sun, Y., Guo, K., Peng, J. &amp; Jiang, Y. Early  blood  pressure  management  in  hemorrhagic  stroke: a meta-analysis. J  Neurol 270, 3369–3376 (2023).</p>
  </li>
  <li>
    <p>Moullaali, T. J. et al. Early  lowering  of  blood  pressure  after  acute  intracerebral  haemorrhage: a systematic  review  and meta-analysis  of  individual  patient data. J  Neurol  Neurosurg  Psychiatry 93, 6–13 (2022).</p>
  </li>
  <li>
    <p>Anderson, C. S., Selim, M. H., Molina, C. A. &amp; Qureshi, A. I. Intensive  Blood  Pressure  Lowering  in  Intracerebral  Hemorrhage. Stroke 48, 2034–2037 (2017).</p>
  </li>
  <li>
    <p>Anderson, C. S. et al. Intensive  blood  pressure  reduction  in  acute  cerebral  haemorrhage  trial (INTERACT): a randomised  pilot  trial. Lancet  Neurol 7, 391–399 (2008).</p>
  </li>
  <li>
    <p>Qureshi, A. I. et al. Intensive  Blood-Pressure  Lowering  in  Patients  with  Acute  Cerebral  Hemorrhage. New  England  Journal  of  Medicine 375, 1033–1043 (2016).</p>
  </li>
  <li>
    <p>Song, L. et al. INTEnsive care bundle  with  blood  pressure  reduction  in  acute  cerebral  hemorrhage  trial (INTERACT3): study  protocol  for a pragmatic  stepped-wedge  cluster-randomized  controlled  trial. Trials 22, 943 (2021).</p>
  </li>
  <li>
    <p>Qureshi, A. I., Mendelow, A. D. &amp; Hanley, D. F. Intracerebral  haemorrhage. The  Lancet 373, 1632–1644 (2009).</p>
  </li>
  <li>
    <p>Anderson, C. S. et al. Rapid  Blood-Pressure  Lowering  in  Patients  with  Acute  Intracerebral  Hemorrhage. New  England  Journal  of  Medicine 368, 2355–2365 (2013).</p>
  </li>
  <li>
    <p>Burns, J., Fisher, J. &amp; Cervantes-Arslanian, A. Recent  Advances  in  the  Acute  Management  of  Intracerebral  Hemorrhage. Neurosurgery  Clinics  of  North America 29, 263–272 (2018).</p>
  </li>
  <li>
    <p>Ma, L. et al. The  third  Intensive Care Bundle  with  Blood  Pressure  Reduction  in  Acute  Cerebral  Haemorrhage  Trial (INTERACT3): an  international, stepped  wedge  cluster  randomised  controlled  trial. The  Lancet 402, 27–40 (2023).</p>
  </li>
</ol>

<p>Lectures: „Evidence  based  management  of  intracerebral  hemorrhage - An  update”, AI Quereshi, 2022</p>

<p>FOAM: INTERACT3, The  sceptics  guide to emergency  medecinte. Pallaci &amp; Hunter.</p>

<p><img src="..%2Fimages%2FINTERACT3_ICH%2FINTERACT3_map.png" alt="INTERACT3_map.png" /></p>]]></content><author><name>Julian Klug</name></author><category term="ICU" /><summary type="html"><![CDATA[Clinical question]]></summary></entry><entry><title type="html">Norepinephrine/Noradrenaline dosing equivalence</title><link href="https://www.julianklug.com/posts/norepinephrine-equivalence" rel="alternate" type="text/html" title="Norepinephrine/Noradrenaline dosing equivalence" /><published>2022-08-08T00:00:00+00:00</published><updated>2022-08-08T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/norepinephrine-equivalence</id><content type="html" xml:base="https://www.julianklug.com/posts/norepinephrine-equivalence"><![CDATA[<p><strong>Gist</strong>: Expression of norepinephrine/noradrenaline dosing is not standardized across countries</p>

<p>Formulations:</p>
<ul>
  <li>noradrenaline tartrate (European Pharmacopoeia)</li>
  <li>noradrenaline acid tartrate (British Pharmacopoeia)</li>
  <li>norepinephrine bitartrate (United States Pharmacopeia)</li>
</ul>

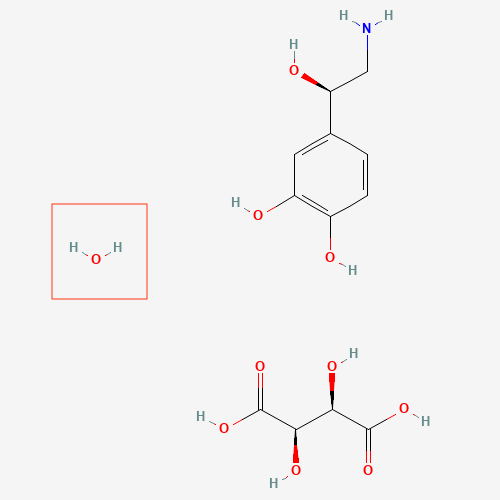
<p>All formulations are equivalent in vasopressor potency (only difference is a H2O molecule added in bitartrate).</p>

<p>Equivalence: 2 mg of norepinephrine bitartrate/tartrate are equivalent to 1 mg of norepinephrine base</p>

<p>Issue: dosing can be expressed as norepinephrine base or specific formulation (e.g. norepinephrine tartrate)</p>
<ul>
  <li>North America: norepinephrine base is the most common expression of dosing</li>
  <li>Europe: norepinephrine tartrate is the most common expression of dosing (but very variable across countries)</li>
</ul>

<p>Thus expression of dosing in Europe is often erroneously twice as high as if expressed in North America. Therefore, caution is required when applying norepinephrine dosing across settings.</p>

<p>Refs:</p>
<ol>
  <li>Leone, M., Goyer, I., Levy, B. et al. Dose of norepinephrine: the devil is in the details. Intensive Care Med 48, 638–640 (2022). https://doi.org/10.1007/s00134-022-06652-x</li>
</ol>

<p><img src="/images/random/Norepinephrine_bitartrate_500.png" alt="Noradrenaline bitartrate" title="Noradrenaline bitartrate" />
<em>Sole difference between noradrenaline tartrate and norepinephrine bitartrate is the extra water molecule in norepinephrine bitartrate</em></p>]]></content><author><name>Julian Klug</name></author><category term="ICU" /><summary type="html"><![CDATA[Gist: Expression of norepinephrine/noradrenaline dosing is not standardized across countries]]></summary></entry><entry><title type="html">Avoiding data leaks on github through jupyter notebooks</title><link href="https://www.julianklug.com/posts/jupyter-notebook-leak" rel="alternate" type="text/html" title="Avoiding data leaks on github through jupyter notebooks" /><published>2022-06-15T00:00:00+00:00</published><updated>2022-06-15T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/jupyter-notebook-leak</id><content type="html" xml:base="https://www.julianklug.com/posts/jupyter-notebook-leak"><![CDATA[<h2 id="a-preventing-a-data-leakage">A. Preventing a data leakage</h2>
<h3 id="clear-all-notebooks-automatically-on-commit">Clear all notebooks automatically on commit</h3>

<p><em>Rationale</em>: run a filter over certain files before they are added to git. This will leave the original file on disk as-is, but commit the “cleaned” version.</p>

<p><strong>1-</strong> Create a .gitattributes file in your repo</p>

<p><strong>.gitattributes:</strong></p>
<div class="language-plaintext highlighter-rouge"><div class="highlight"><pre class="highlight"><code>*.ipynb filter=jupyternotebook
</code></pre></div></div>

<p><strong>2-</strong> Create a .gitconfig file in your repo</p>

<p><strong>.gitconfig:</strong></p>
<div class="language-plaintext highlighter-rouge"><div class="highlight"><pre class="highlight"><code>[filter "jupyternotebook"]
        clean = jupyter nbconvert --to=notebook --ClearOutputPreprocessor.enabled=True --stdout %f
        required
        smudge = cat
</code></pre></div></div>

<p><strong>3-</strong> Add custom .gitconfig to local git config: <code class="language-plaintext highlighter-rouge">git config --local include.path ../.gitconfig</code></p>
<ul>
  <li><strong>N.B.</strong>: this step has to be repeated every time the repo is cloned.</li>
</ul>

<p><strong>4-</strong> Verify that custom config was added to local git config</p>

<p>–&gt; This hook should be run every time a file is added (<code class="language-plaintext highlighter-rouge">git add</code>)</p>

<p><strong>.git/config:</strong></p>
<div class="language-plaintext highlighter-rouge"><div class="highlight"><pre class="highlight"><code>...
[include]
        path = ../.gitconfig
</code></pre></div></div>

<h3 id="use-github-actions-to-prevent-committing-executed-notebooks">Use github actions to prevent committing executed notebooks</h3>

<p><em>Rationale</em>: Prevent accidental commits of executed notebooks by checking every push with github actions.</p>

<ol>
  <li>Create a .github/workflows/main.yml file in your repo</li>
</ol>

<p><strong>.github/workflows/main.yml:</strong></p>
<div class="language-yaml highlighter-rouge"><div class="highlight"><pre class="highlight"><code><span class="na">name</span><span class="pi">:</span> <span class="s">GitHub Pre-Push actions</span>
<span class="na">on</span><span class="pi">:</span> <span class="pi">[</span><span class="nv">push</span><span class="pi">]</span>
<span class="na">jobs</span><span class="pi">:</span>
  <span class="na">ensure_clean_jupyter_notebooks</span><span class="pi">:</span>
    <span class="na">runs-on</span><span class="pi">:</span> <span class="s">ubuntu-latest</span>
    <span class="na">steps</span><span class="pi">:</span>
    <span class="pi">-</span> <span class="na">uses</span><span class="pi">:</span> <span class="s">ResearchSoftwareActions/EnsureCleanNotebooksAction@1.1</span>
      <span class="na">with</span><span class="pi">:</span>
        <span class="na">disable-checks</span><span class="pi">:</span> <span class="s">execution_count</span>
</code></pre></div></div>

<p>This action is provided by <a href="https://github.com/marketplace/actions/ensure-clean-jupyter-notebooks">ResearchSoftwareActions</a>.</p>

<h2 id="b-in-case-of-a-data-leak-already-on-github">B. In case of a data leak already on github</h2>
<h3 id="clear-all-notebooks">Clear all notebooks</h3>
<p>Whilst in the repo:</p>

<p><code class="language-plaintext highlighter-rouge">jupyter nbconvert --ClearOutputPreprocessor.enabled=True --inplace */*/*/*/*/*.ipynb</code>
(or nbconvert &gt; 6.0: <code class="language-plaintext highlighter-rouge">jupyter nbconvert --clear-output --inplace */*/*/*/*/*.ipynb</code>)</p>

<p>where one should start from <code class="language-plaintext highlighter-rouge">*.ipynb</code> to as deep as your repo structure goes (<code class="language-plaintext highlighter-rouge">*/*/*/*/*/*</code>) in this case</p>

<h3 id="clean-all-jupyter-notebooks-already-on-github">Clean all jupyter notebooks already on github</h3>

<p>Requirements: <a href="https://rtyley.github.io/bfg-repo-cleaner/">BFG</a> (can be installed via brew)</p>

<p>Procedure as explained in <a href="https://rtyley.github.io/bfg-repo-cleaner/">this blog post</a>.</p>
<ol>
  <li>Remove your old local repo folder (keep it temporarily save): <code class="language-plaintext highlighter-rouge">mv example-repo example-repo-old</code></li>
  <li>Clone in mirror repo: <code class="language-plaintext highlighter-rouge">git clone --mirror git@github.com:example/example-repo.git</code></li>
  <li><strong>Target all jupyter notebooks of repo</strong>: <code class="language-plaintext highlighter-rouge">bfg --delete-files "{*.ipynb}" example-repo.git/</code></li>
  <li>Rewrite history: <code class="language-plaintext highlighter-rouge">cd example-repo &amp;&amp; git reflog expire --expire=now --all &amp;&amp; git gc --prune=now --aggressive</code></li>
  <li><code class="language-plaintext highlighter-rouge">git push</code></li>
  <li>Delete mirror repo (as well as your temporary copy of the old version): <code class="language-plaintext highlighter-rouge">cd ../ &amp;&amp; rm -rf example-repo.git</code></li>
  <li>Re-download the clean version of the repo: <code class="language-plaintext highlighter-rouge">git clone git@github.com:example/example-repo.git</code></li>
  <li><strong>Repeat step 3 and 4 of part A.</strong> (reinstaure custom filter after cloning)</li>
</ol>

<p>This essentially removes all history of these files.</p>]]></content><author><name>Julian Klug</name></author><category term="python" /><summary type="html"><![CDATA[A. Preventing a data leakage Clear all notebooks automatically on commit]]></summary></entry><entry><title type="html">Preparing for a second attack</title><link href="https://www.julianklug.com/posts/research/Stroke-Resilience/" rel="alternate" type="text/html" title="Preparing for a second attack" /><published>2022-06-09T00:00:00+00:00</published><updated>2022-06-09T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/research/Stroke-Resilience</id><content type="html" xml:base="https://www.julianklug.com/posts/research/Stroke-Resilience/"><![CDATA[<blockquote>
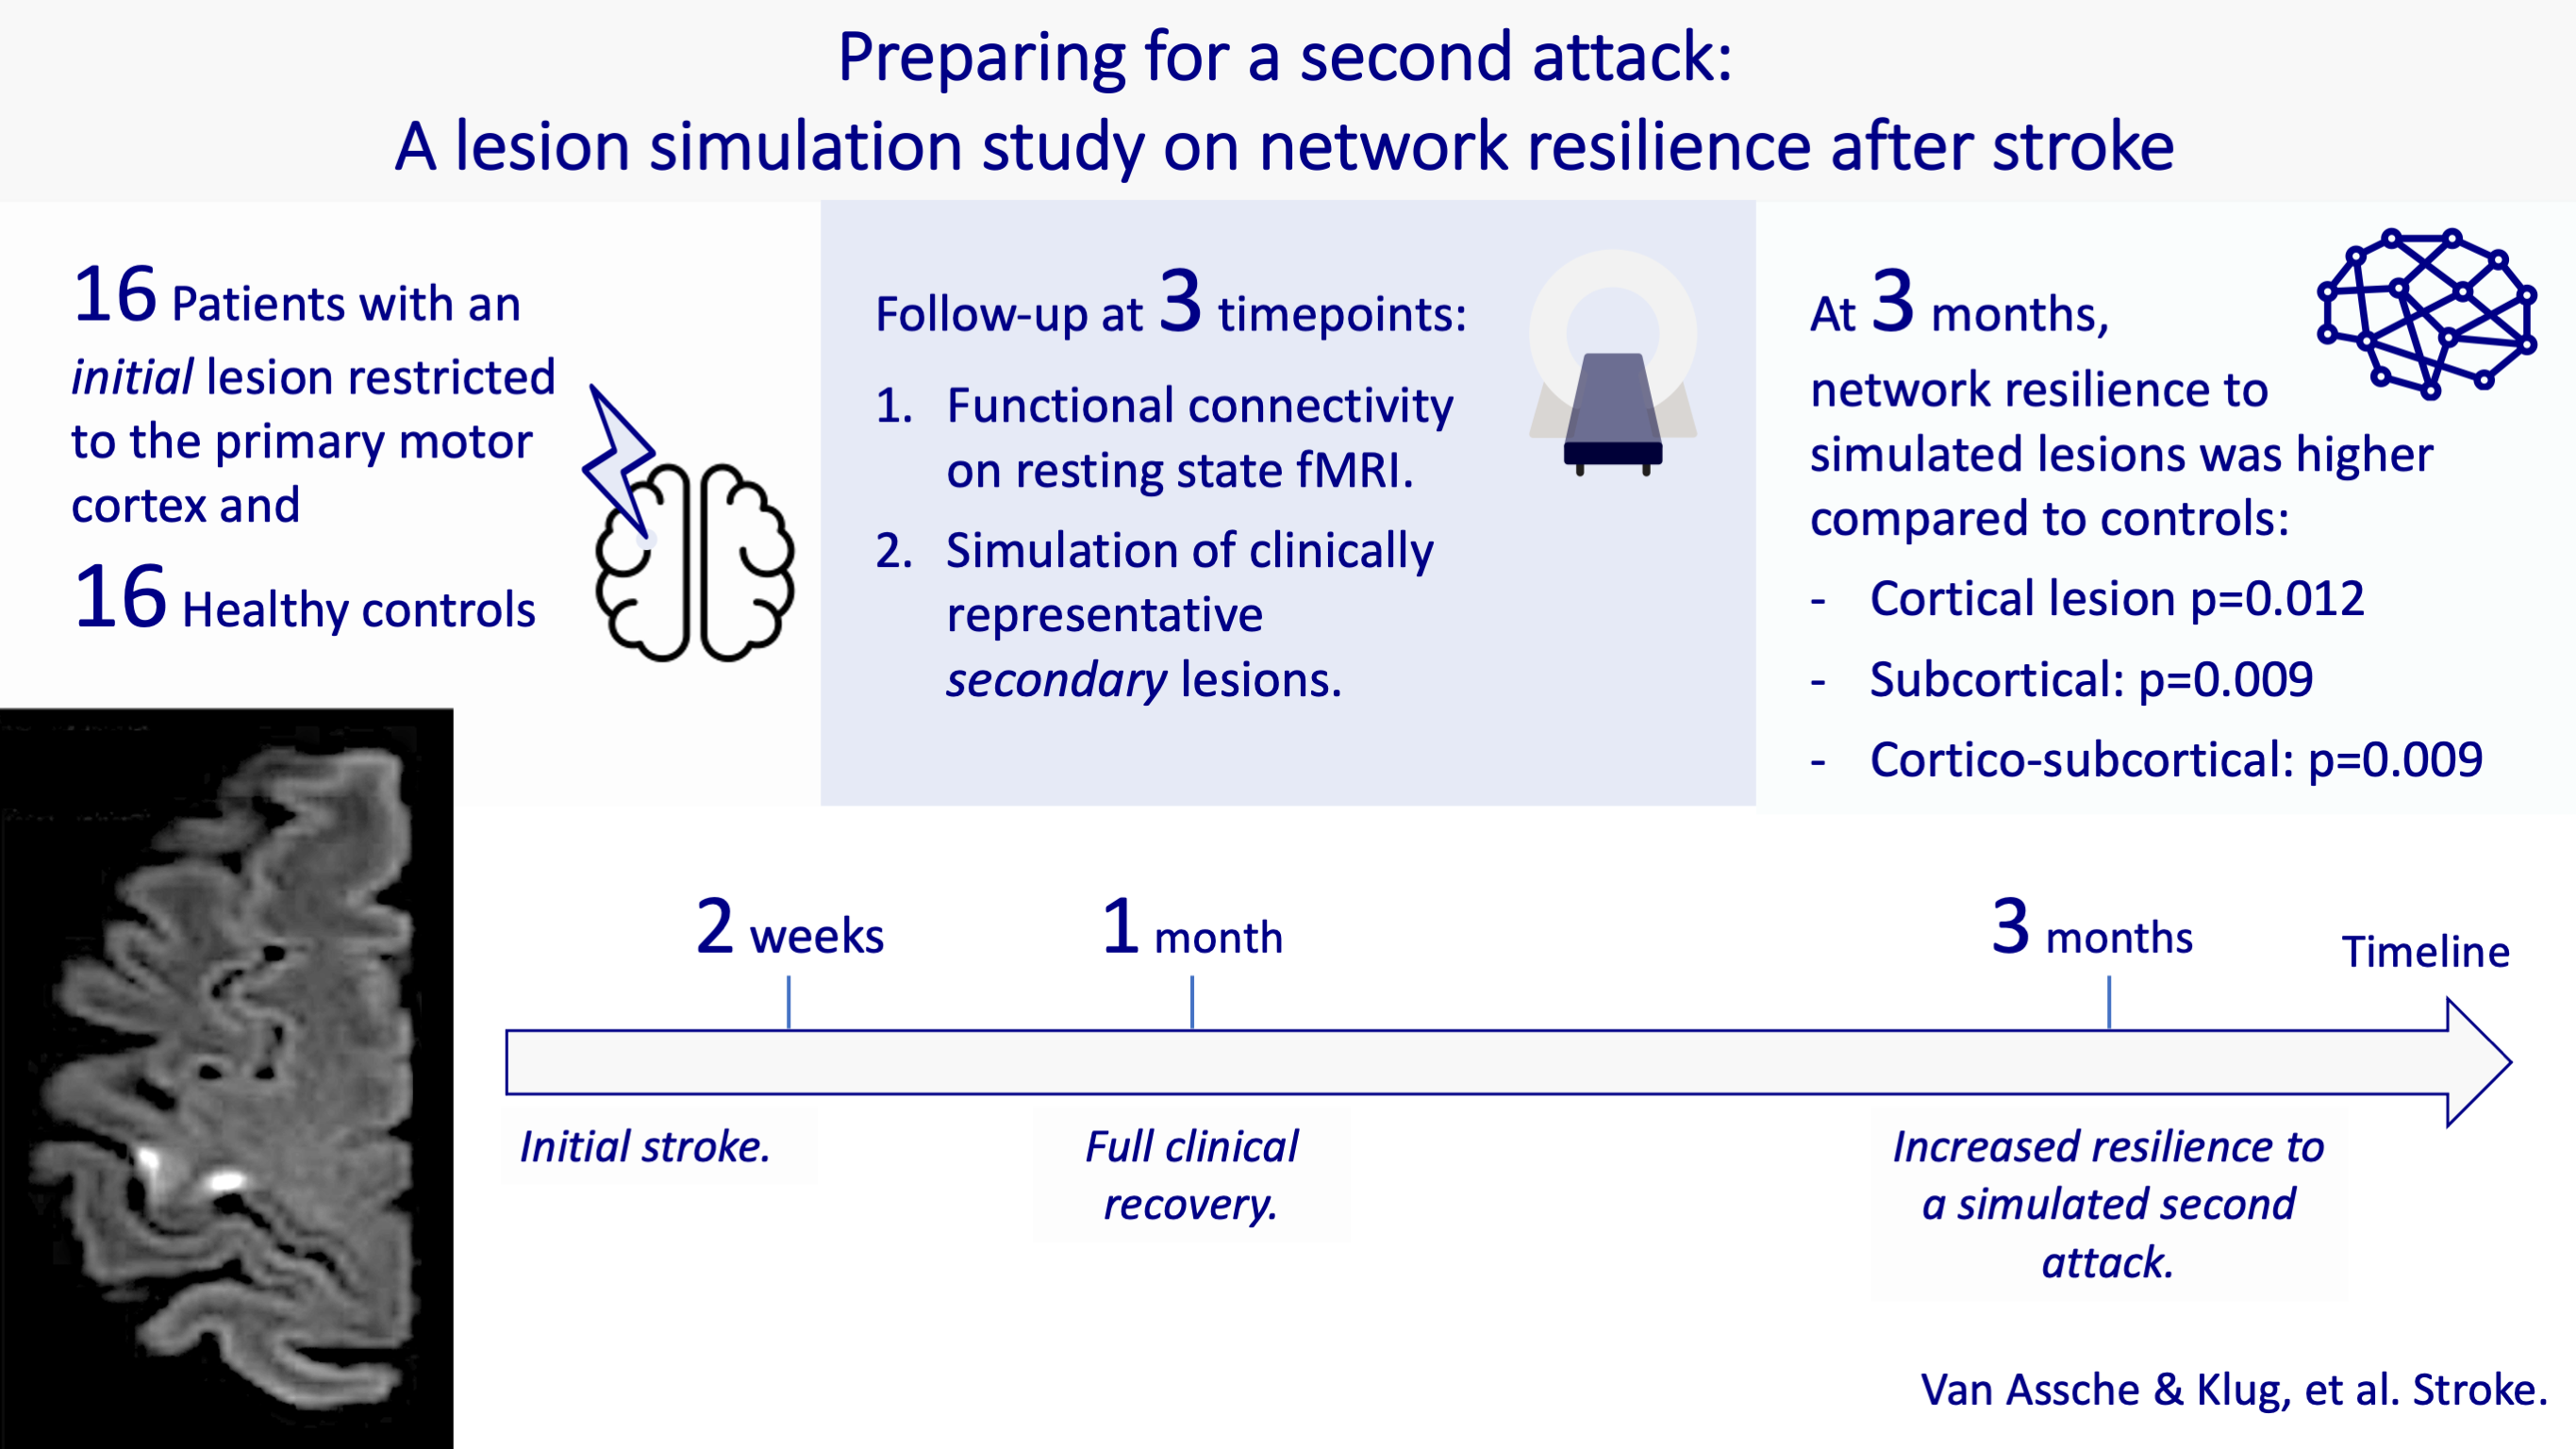
  <p>𝗢𝘂𝗿 𝗵𝘆𝗽𝗼𝘁𝗵𝗲𝘀𝗶𝘀: the brain becomes more resilient to a second stroke after a first attack</p>
</blockquote>

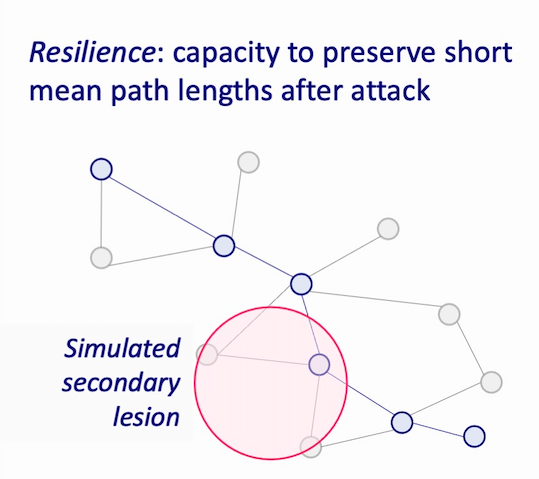
<p>To be able to measure resilience of neural networks observed on resting state fMRI we define it as the capacity to preserve short mean path lenghts after an attack.</p>

<p><img src="/images/stroke_resilience/resilience_def.png" alt="Resilience" title="Resilience" /></p>

<p>𝗣𝗼𝗽𝘂𝗹𝗮𝘁𝗶𝗼𝗻:</p>
<ul>
  <li>16 patients with an initial lesion restricted to M1 and full recovery at 1 month</li>
  <li>16 healthy controls</li>
</ul>

<p>–&gt; All patients had a fMRI scan at 3 timepoints (2 weeks, 1 month and 3 months after stroke)</p>

<p>𝗜𝗻𝘁𝗲𝗿𝘃𝗲𝗻𝘁𝗶𝗼𝗻: simulation of clinically representative secondary lesions on the obtained functional networks</p>

<p>𝗥𝗲𝘀𝘂𝗹𝘁𝘀: after full clinical recovery, the networks of patients having sustained a stroke 3 months beforehand were more resilient to a secondary attack</p>

<p><em>Full paper</em>: Mitsouko Assche, Julian Klug, Elisabeth Dirren, Jonas Richiardi, Emmanuel Carrera, “Preparing for a Second Attack: A Lesion Simulation Study on Network Resilience After Stroke.” Stroke, 2022</p>

<h5 id="code-availability">Code availability</h5>

<p>All code is available at <a href="https://github.com/JulianKlug/stroke-resilience" title="JK's Github">my github</a>.</p>

<p><img src="/images/stroke_resilience/graphical_abstract_big_text.png" alt="Resilience" title="Resilience" /></p>]]></content><author><name>Julian Klug</name></author><category term="research" /><summary type="html"><![CDATA[𝗢𝘂𝗿 𝗵𝘆𝗽𝗼𝘁𝗵𝗲𝘀𝗶𝘀: the brain becomes more resilient to a second stroke after a first attack]]></summary></entry><entry><title type="html">An Approach to Diffusion Tensor Imaging of Auditory Brainstem Implant Candidates</title><link href="https://www.julianklug.com/posts/research/ABI-DTI/" rel="alternate" type="text/html" title="An Approach to Diffusion Tensor Imaging of Auditory Brainstem Implant Candidates" /><published>2017-09-20T00:00:00+00:00</published><updated>2017-09-20T00:00:00+00:00</updated><id>https://www.julianklug.com/posts/research/ABI-DTI</id><content type="html" xml:base="https://www.julianklug.com/posts/research/ABI-DTI/"><![CDATA[<h2 id="context">Context</h2>

<blockquote>
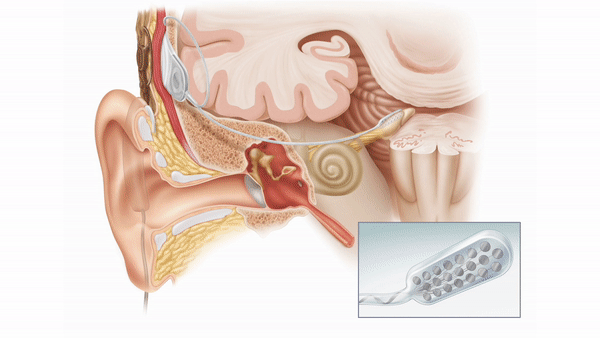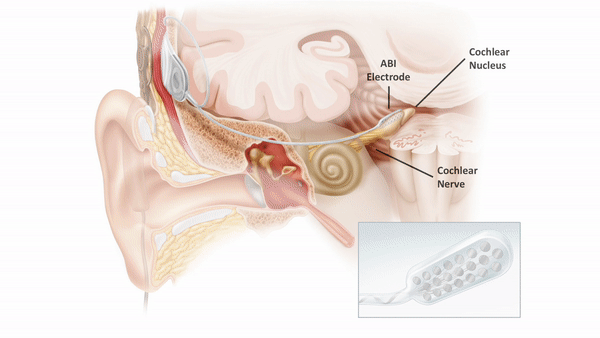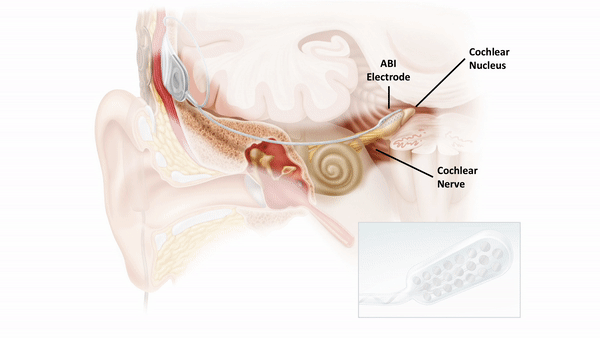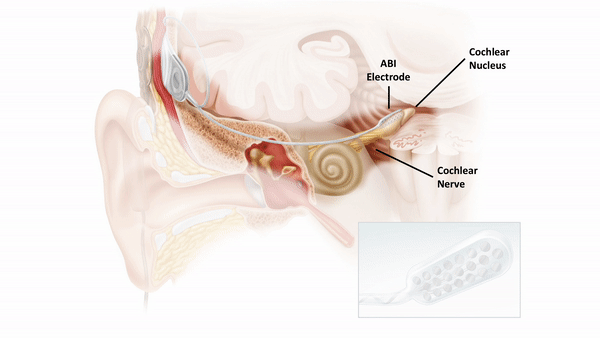
  <h4 id="what-is-an-abi">What is an ABI?</h4>
</blockquote>

<p>The auditory brainstem implant (ABI) provides sound detection for patients who are not candidates for a cochlear implant due to anatomic constraints.
The ABI bypasses the cochlea and cochlear nerve to electrically stimulate second order auditory neurons of the cochlear nucleus (found in the pontomedullary junction of the brainstem).</p>

<p><img src="/images/abi_dti/ABI_anatomy.gif" alt="ABI Anatomy" title="ABI Anatomy" /></p>

<p>Unfortunately, hearing outcomes among ABI recipients remain highly variable and performance lags significantly behind cochlear implant users. Anatomic differences, including size of the residual cochlear nerve or presence of a cerebellopontine angle tumor, as well as differences in electrode position may influence audiometric outcomes.</p>

<p>Prior research also suggests that white matter organization, when visualized with diffusion tensor imaging, correlates with auditory performance in patients with cochlear implants. Diffusion tensor imaging (DTI) provides a specific type of modeling data to reveal structural integrity of white matter in vivo by detecting the quantity and directionality of water diffusion. Quantitative analysis of white matter microstructure using DTI may enable greater insight into ABI outcomes perioperatively.</p>

<p>However, ABI candidates, especially those affected by Neurofibromatosis type 2 (NF2), represent a particular challenge for the visualization of white matter tracts due to deformities in the posterior fossa from large tumor load and hardware such as auditory implants and cranioplasty material.</p>

<p><img src="/images/abi_dti/Schwannoma.gif" alt="Schwannoma" title="Schwannoma" /></p>

<h3 id="aim">Aim</h3>

<p>The aim of this study was to examine the feasibility of utilizing DTI to assess white matter microstructures along the auditory pathways in ABI candidates.</p>

<h3 id="methods">Methods</h3>

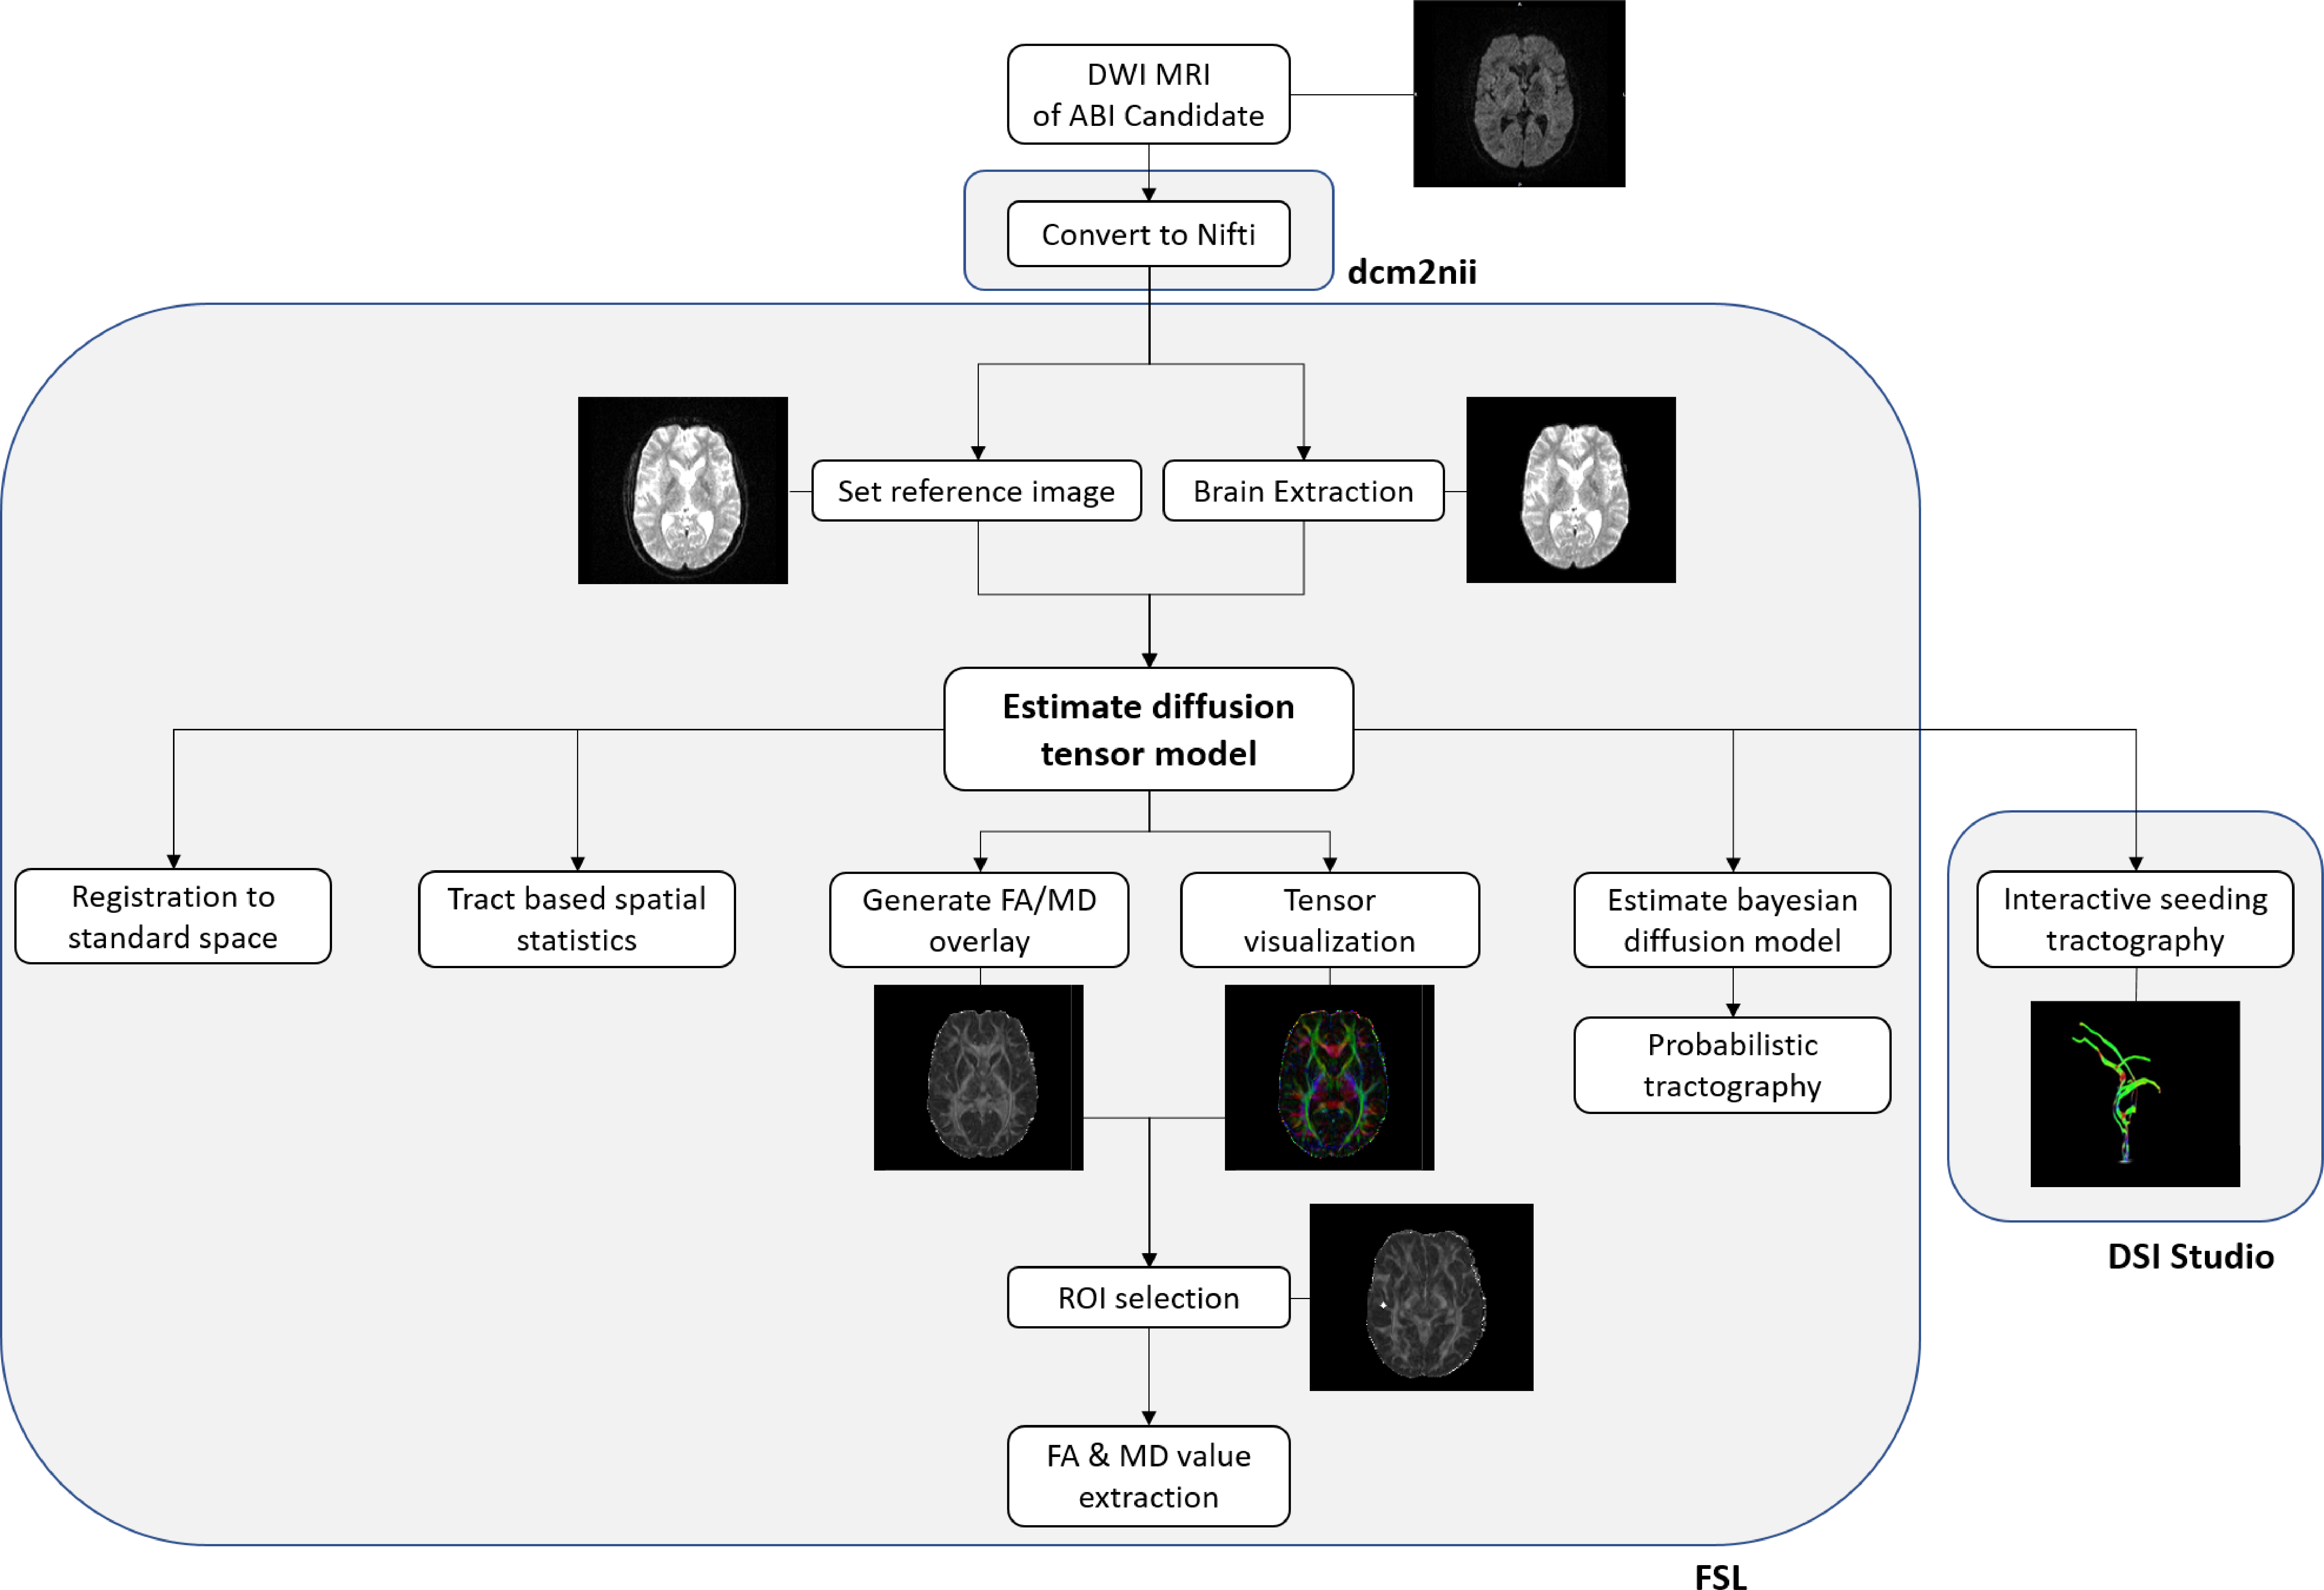
<p>A total of eight patients diagnosed with NF2 were implanted and scanned perioperatively. The diffusion weighed sequences were imported and registered to standard space. After removing all non-brain tissue, diffusion tensors were estimated, and FA and MD values were extracted on selected regions of interest (ROIs).</p>

<p><img src="/images/abi_dti/methods.jpg" alt="Methods" title="Methods" /></p>

<h3 id="results">Results</h3>

<ul class="task-list">
  <li class="task-list-item"><input type="checkbox" class="task-list-item-checkbox" disabled="disabled" checked="checked" />ROIs were extracted and DTI indices could be measured in 76% of subjects</li>
  <li class="task-list-item"><input type="checkbox" class="task-list-item-checkbox" disabled="disabled" checked="checked" />Fiber tracking could be performed</li>
  <li class="task-list-item"><input type="checkbox" class="task-list-item-checkbox" disabled="disabled" checked="checked" />Limitations were identified</li>
</ul>

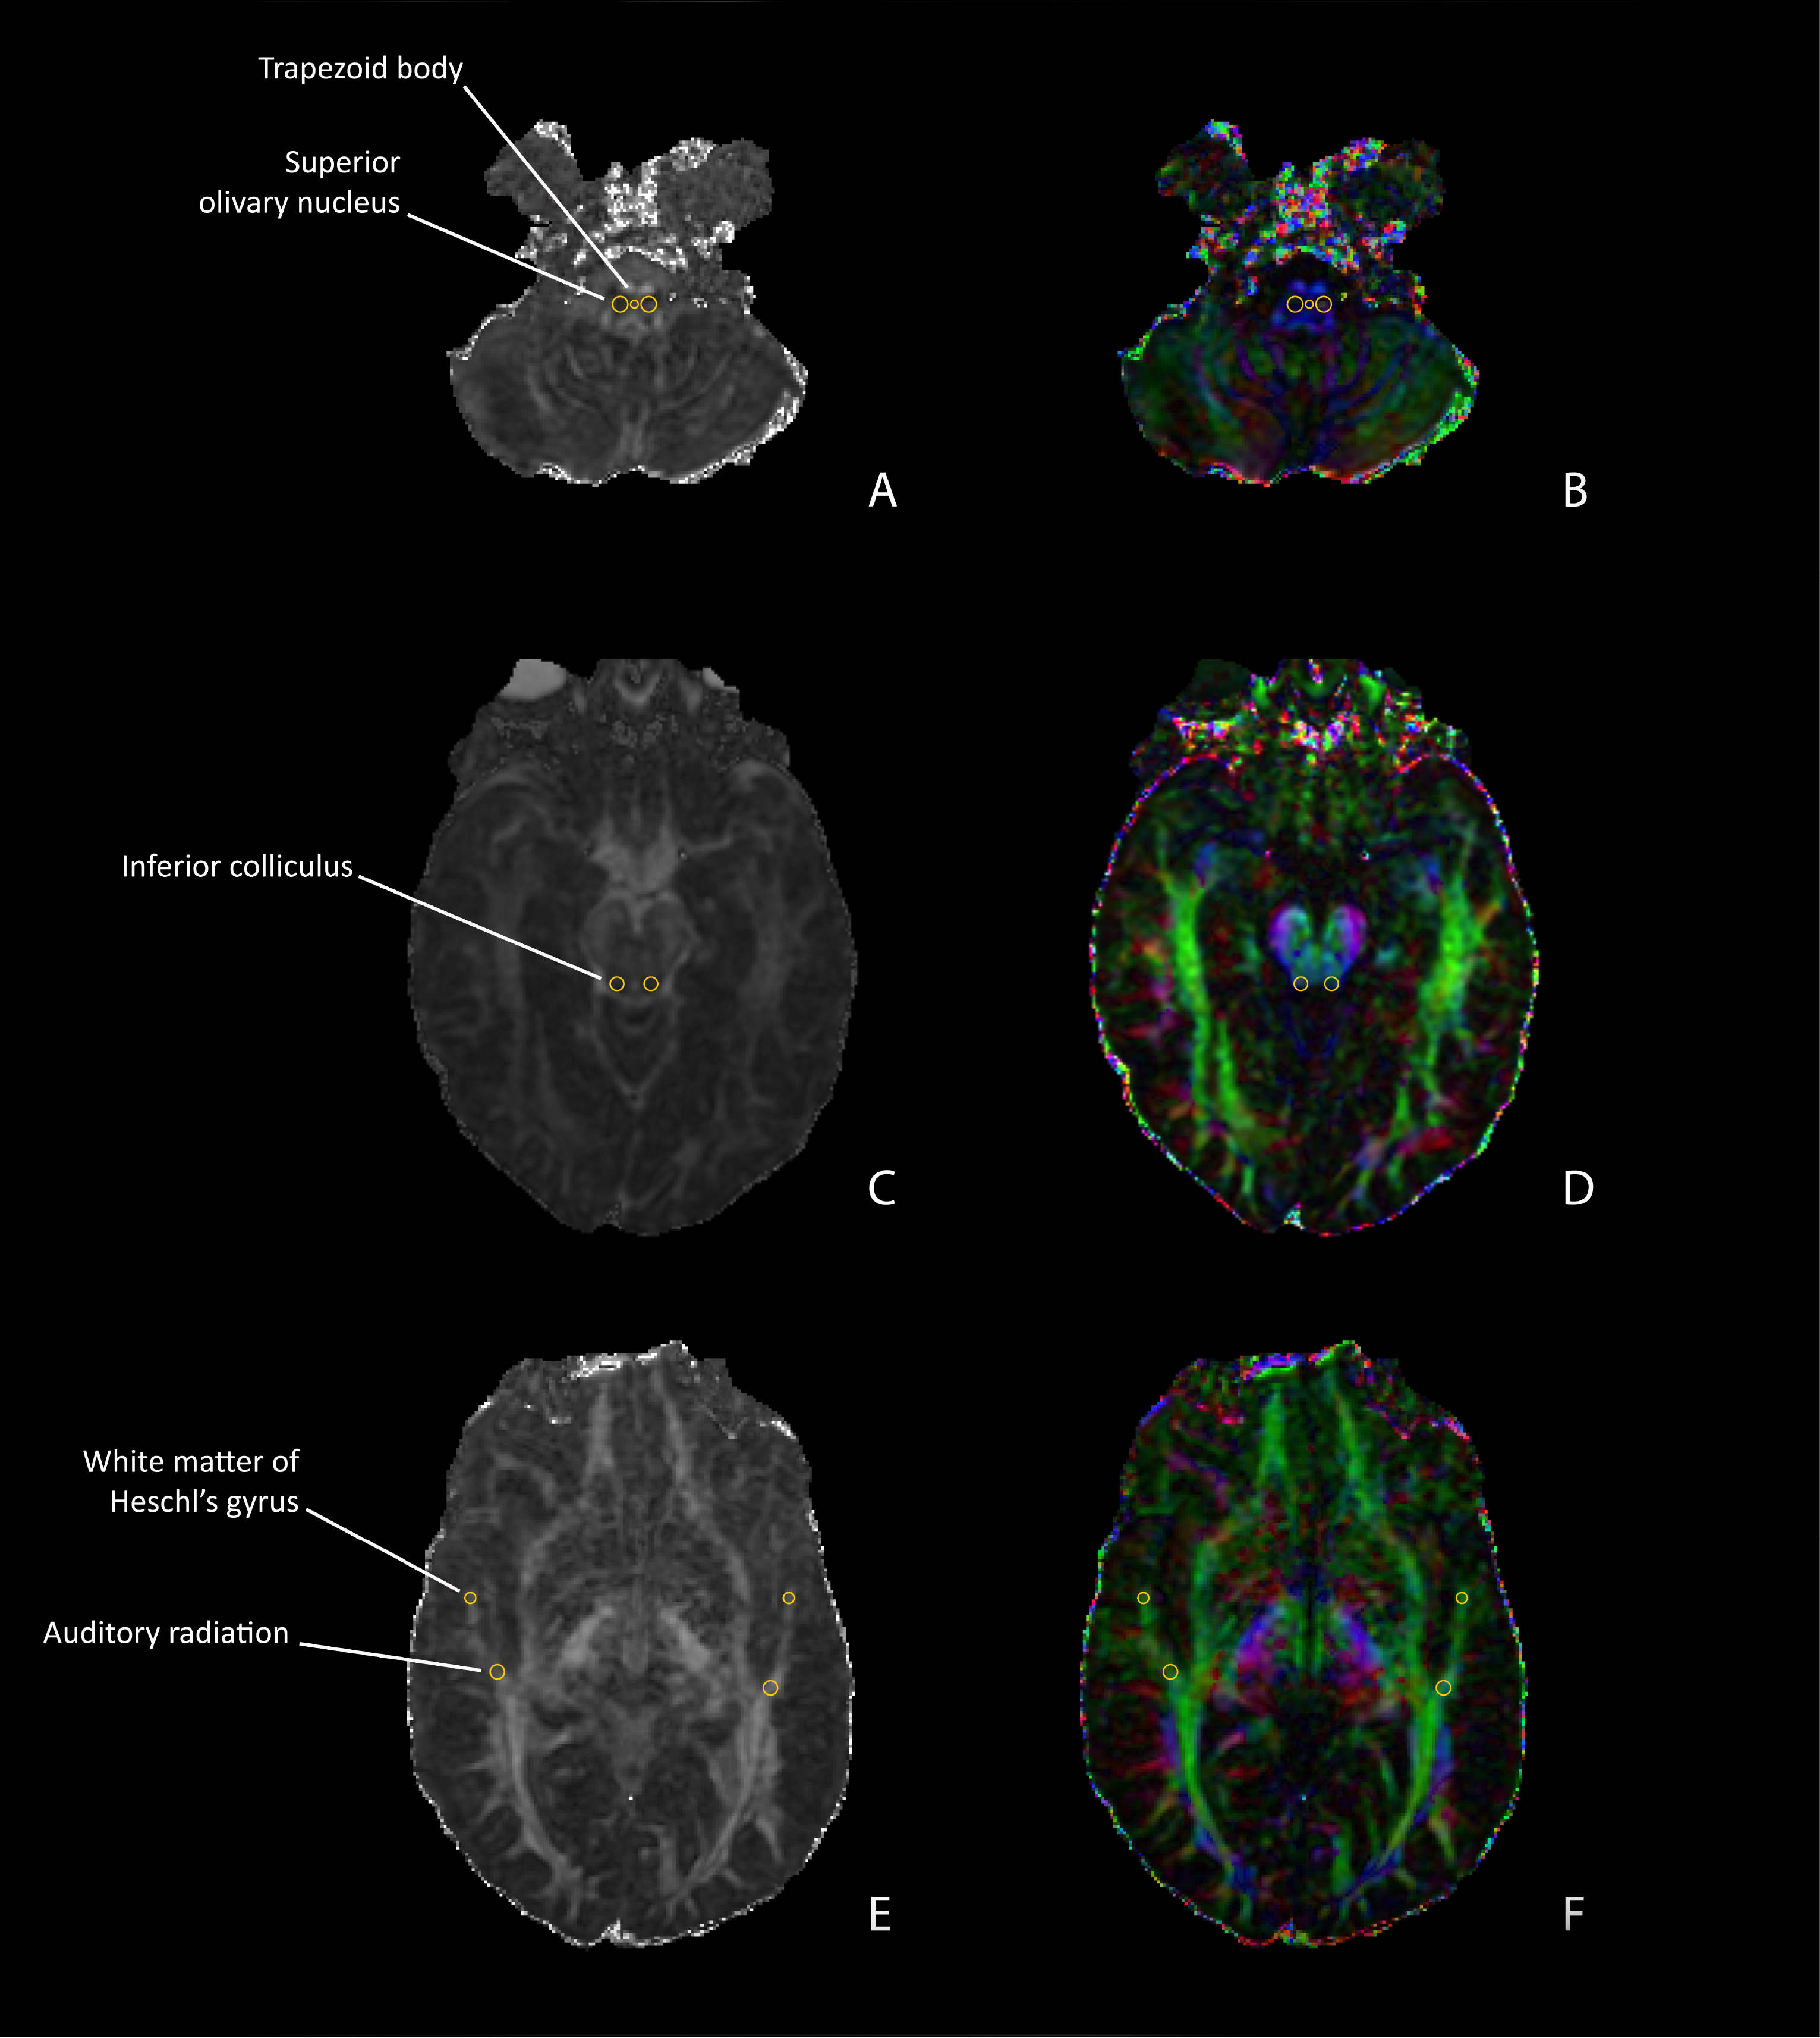
<p><img src="/images/abi_dti/ROIs.jpg" alt="ROIs" title="ROIs" />
<em>Representative DTI scans (left: FA/MD overlap map; right: FA-modulated vector map) of selected ROIs. A. Trapezoid body and superior olivary nuclei. B. Inferior colliculi. C. Auditory radiations and white matter of Heschl’s gyrus.</em></p>

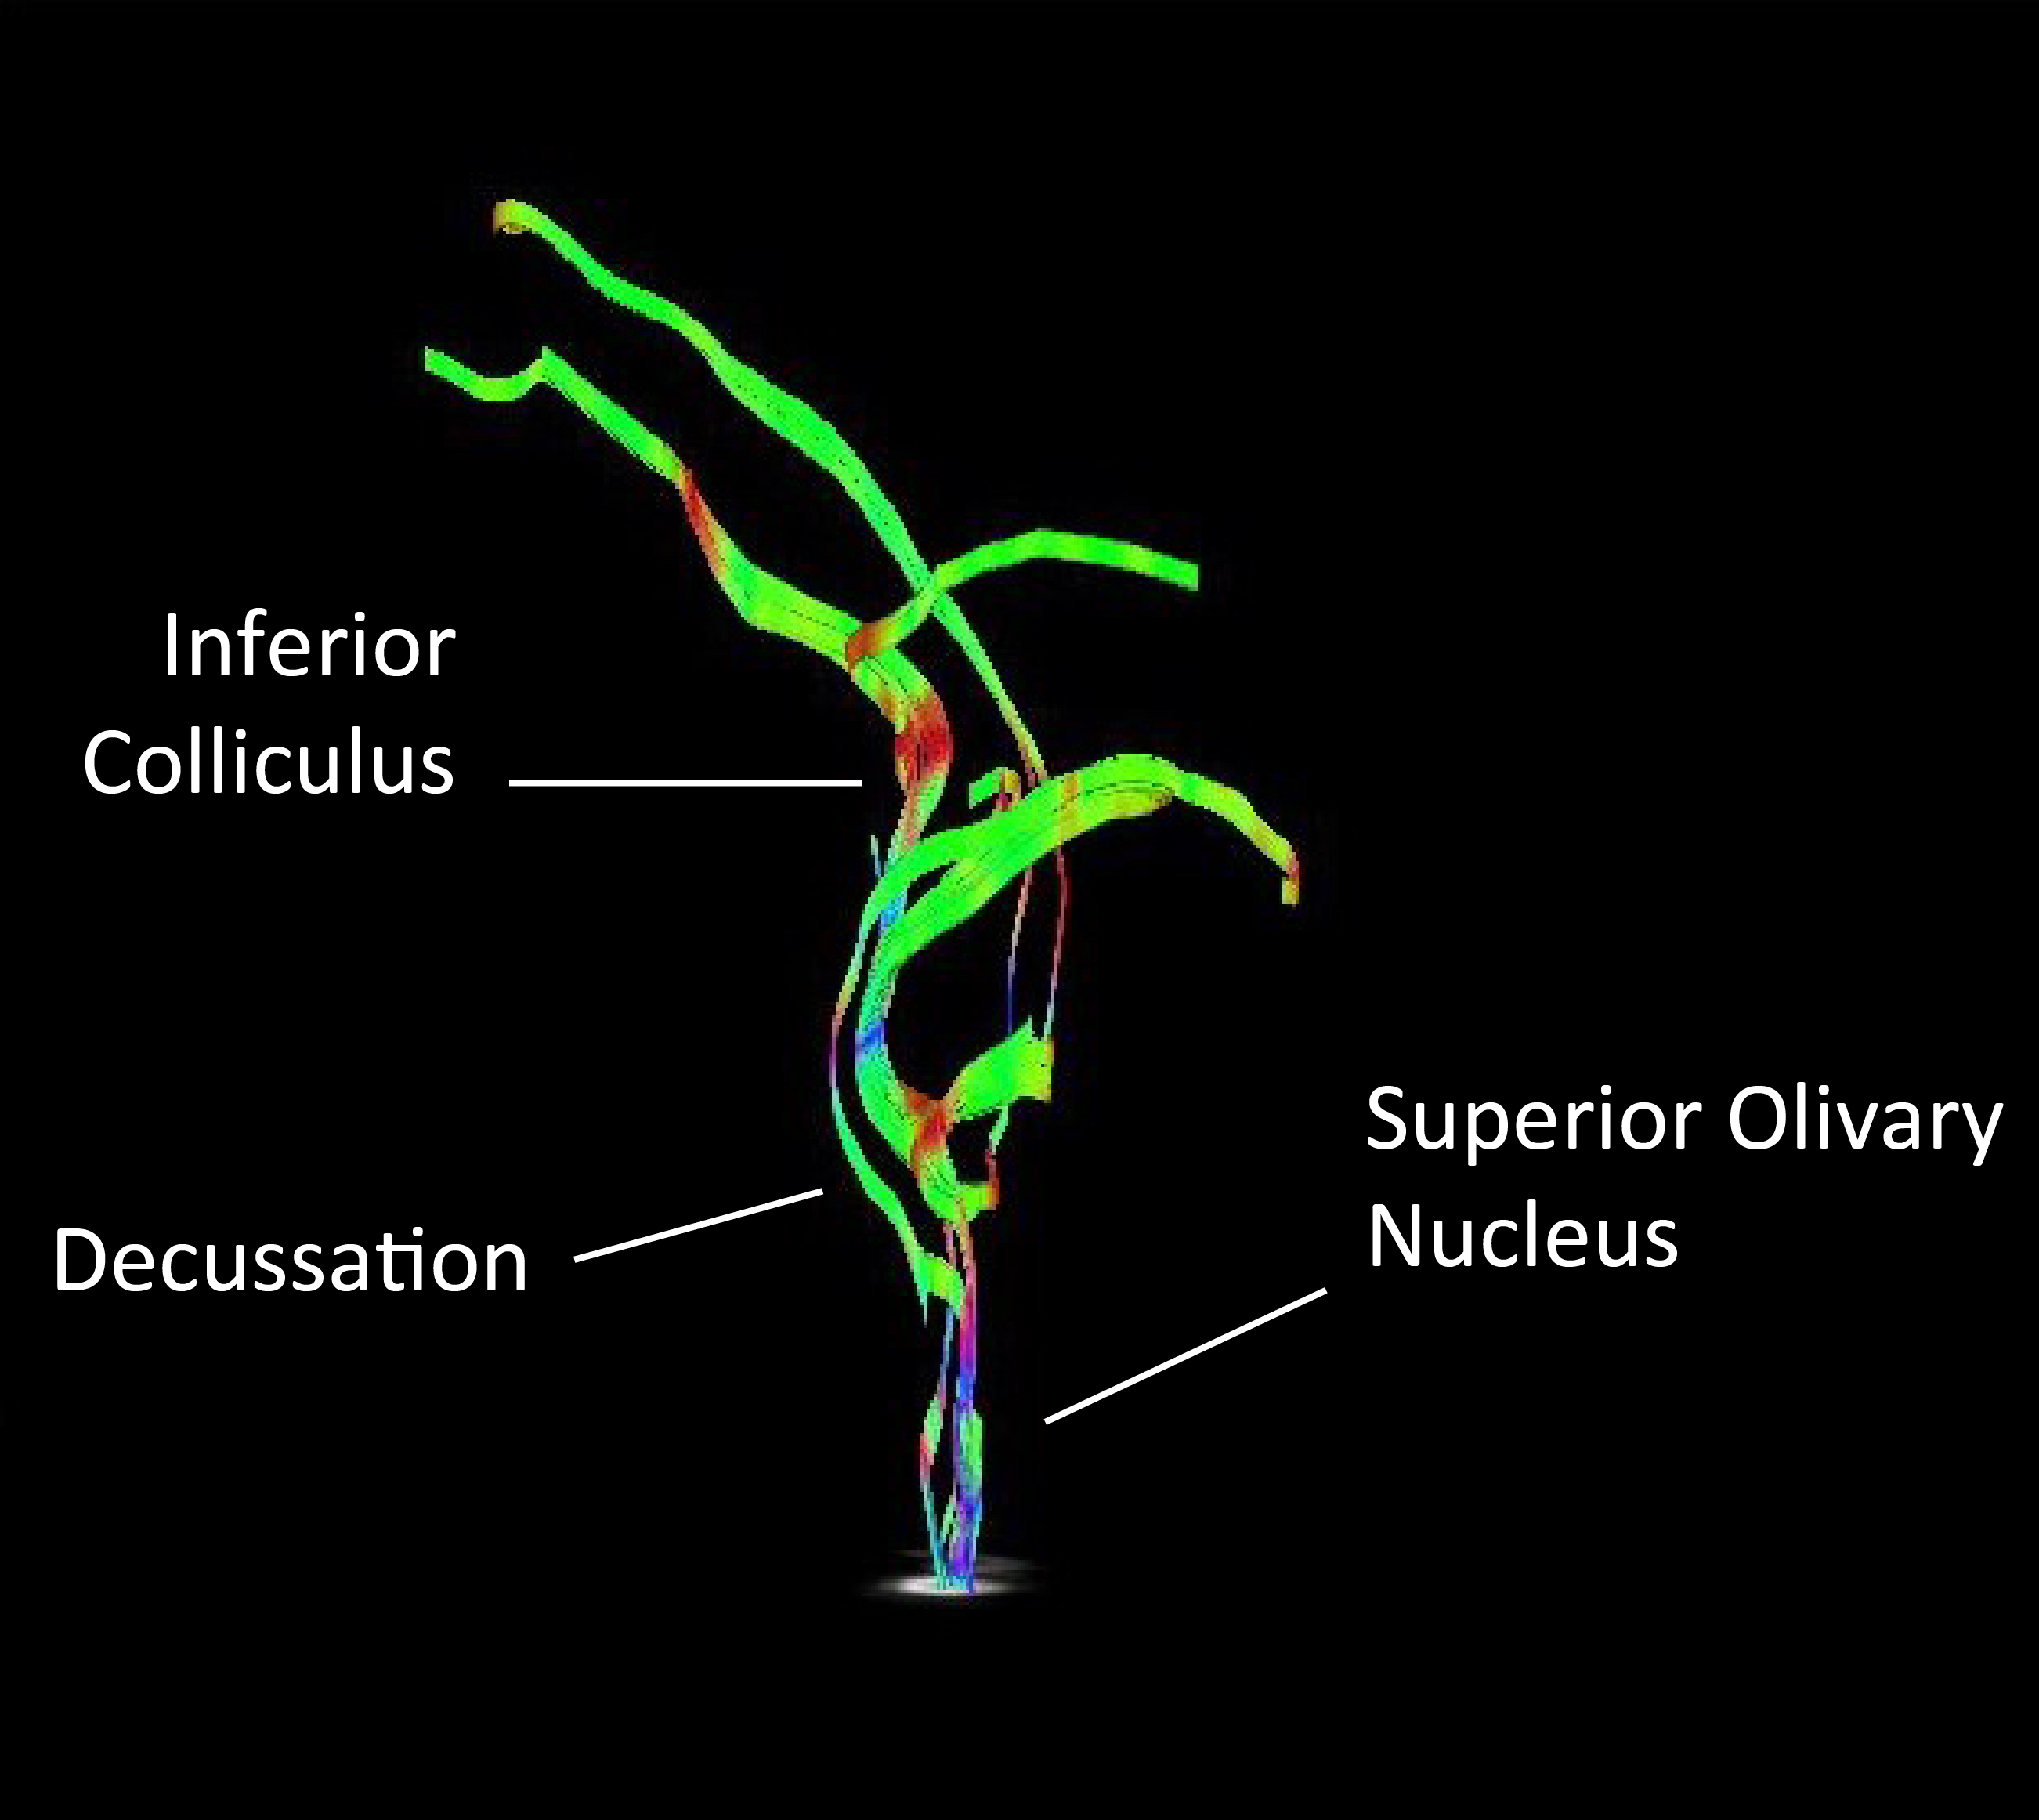
<p><img src="/images/abi_dti/Tracto.jpg" alt="Tractography" title="Tractography" />
<em>Representative tractography of fibers originating in the superior olivary nucleus (coronal view). Tracts decussating before reaching the contralateral inferior colliculus can be visualized.</em></p>

<p><img src="/images/abi_dti/limitations.jpg" alt="Limitations" title="Limitations" />
<em>Representative FA/MD overlay maps for ROIs with missing values (axial view). A. Susceptibility artifact due to left cochlear implant. B. Susceptibility artifact due to right ABI. C. Tumor (dotted line) compressing brainstem.</em></p>

<h3 id="discussion">Discussion</h3>

<p>At the time, this was the first study to describe the use of DTI in candidates for the ABI in a clinical setting, allowing the measure of FA and MD at specific ROIs along the auditory pathway. This matters, as earlier studies by Huang and colleagues have shown that FA values of the same ROIs correlate with auditory outcome after cochlear implantation. Combined with the approach described here, this suggests the possibility for a tool to predict ABI outcomes preoperatively. Moreover, Scholz et al. describe the effect of motor training on FA measures on selected ROIs. Applying this methodology to ABI users would allow to gain great insight to the physiological changes following implantation and might hint to further possibilities to enhance postoperative adaptation.</p>

<h3 id="limitations">Limitations</h3>
<ul>
  <li>Small sample size</li>
  <li>Inconsistent DTI availability</li>
  <li>Low DTI resolution</li>
</ul>

<h3 id="conclusions">Conclusions</h3>

<table>
  <thead>
    <tr>
      <th><strong>Technique</strong></th>
      <th><strong>Utility</strong></th>
      <th><strong>Feasibility in ABI patients</strong></th>
    </tr>
  </thead>
  <tbody>
    <tr>
      <td>FA/MD measures</td>
      <td>Quantitative analysis (ROIs)</td>
      <td>Yes</td>
    </tr>
    <tr>
      <td>FA-modulated vector map	 </td>
      <td>Visualization of fiber direction</td>
      <td>Yes</td>
    </tr>
    <tr>
      <td>Whole Brain Image Registration</td>
      <td>Comparative analysis</td>
      <td>No</td>
    </tr>
    <tr>
      <td>Tract-Based Spatial Statistics</td>
      <td>Quantitative analysis (whole brain)</td>
      <td>No</td>
    </tr>
    <tr>
      <td>Tractography</td>
      <td>Qualitative analysis &amp; Tract visualization</td>
      <td>Yes</td>
    </tr>
  </tbody>
</table>

<p><em>Feasibility of diffusion tensor imaging techniques and measures in ABI candidates</em></p>

<h3 id="personal-context">Personal Context</h3>

<p>I worked on this project during my time at the <a href="https://scholar.harvard.edu/leebrownlab/home" title="Lee/Brown">Lee/Brown lab</a>, Harvard/MEEI, with the continuous support of <a href="https://oto.hms.harvard.edu/people/vivek-kanumuri" title="V. Kanumuri">V. Kanumuri, MD</a>. In the end, I never had the occasion to fully complete and publish it.</p>

<h3 id="code-availability">Code availability</h3>

<p>All code is available at <a href="https://github.com/MonsieurWave/DTI-Scripts" title="JK's Github">my github</a>. It is mostly based on FSL.</p>

<p>If you are interested in reading the original paper, don’t hesitate to contact me.</p>

<h3 id="video-summary">Video Summary</h3>

<iframe width="560" height="315" src="https://www.youtube.com/embed/9QndBLhxEVo" frameborder="0" allow="accelerometer; autoplay; clipboard-write; encrypted-media; gyroscope; picture-in-picture" allowfullscreen=""></iframe>
<h3 id="references">References</h3>

<ol>
  <li>Smith SM, Jenkinson M, Woolrich MW, Beckmann CF, Behrens TEJ, Johansen-Berg H, et al. Advances in functional and structural MR image analysis and implementation as FSL. Neuroimage. 2004;23 Suppl 1:S208-219.</li>
  <li>Huang L, Zheng W, Wu C, Wei X, Wu X, Wang Y, et al. Diffusion Tensor Imaging of the Auditory Neural Pathway for Clinical Outcome of Cochlear Implantation in Pediatric Congenital Sensorineural Hearing Loss Patients. PLoS ONE. 2015;10(10):e0140643.</li>
  <li>Scholz J, Klein MC, Behrens TEJ, Johansen-Berg H. Training induces changes in white-matter architecture. Nat Neurosci. 2009 Nov;12(11):1370–1.</li>
  <li>Potthoff, M. (2013). ABI how it works image [image format]. retrieved from http://newsroom.hei.org/news/fda-approves-clinical-trial-of-242830</li>
</ol>]]></content><author><name>Julian Klug</name></author><category term="research" /><summary type="html"><![CDATA[Context]]></summary></entry></feed>